
Research Studies
Study Tracker
A 40-year decline in permanent-tooth caries among 12-year-olds in Japan in the absence of systemic fluoride-based prevention: public health.Abstract
Full-text original article online at
https://link.springer.com/article/10.1186/s12889-026-27836-w
Objectives
To re-examine Japan’s long-term decline in permanent-tooth caries among 12-year-olds and assess its implications for population-level caries prevention beyond historically dominant systemic fluoride-centered prevention frameworks.
Study design
Ecological analysis of national surveillance data.
Methods
We assembled long-term nationwide data from Japan on caries experience in 12-year-olds. Data were derived from standardized school dental examinations with high coverage and low temporal variability. Trends were examined descriptively and interpreted in relation to historically established systemic fluoride–caries prevention frameworks, including population fluoride exposure and long-term changes in sugar availability.
Results
Japan experienced a near-continuous decline in caries among 12-year-olds over approximately 40 years, reaching a national mean DMFT of 0.53 in 2023—well below levels historically reported in populations exposed to systemic fluoride through community water fluoridation. This decline occurred without community water fluoridation and largely before the approval of high-fluoride toothpaste in 2017 and its recommendation for school-aged children in 2023. Although sugar availability declined early, caries levels continued to fall long after sugar intake stabilized.
Conclusions
Japan represents a rare natural social experiment demonstrating that sustained population-level caries reduction can occur through cumulative non-systemic fluoride pathways. These findings suggest fluoride-centered frameworks alone may not fully explain long-term population trends and support a broader multicausal approach to caries prevention. They may inform population-level oral health strategies in settings where reliance on systemic fluoride alone may be insufficient.
Introduction — the global paradox
Dental caries remains a major public health problem worldwide [1]. Despite decades of investment in fluoride-based prevention strategies [2,3,4], substantial differences in caries experience persist across countries [1, 3], indicating that fluoride exposure alone cannot fully explain long-term population-level trends in caries.
Over several decades, Japan has experienced a sustained and unusually well-documented decline in permanent-tooth caries among 12-years olds [5,6,7]. This decline has been captured through nationwide, standardized school dental examinations with exceptionally high coverage and temporal stability, providing a rare opportunity to examine long-term population trends with minimal measurement noise [5].
Importantly, this trajectory unfolded in the absence of nationwide community water fluoridation [2] and largely preceded both the approval of high-fluoride toothpaste in 2017 [8] and its recommendation for children of school age in 2023. Consequently, Japan’s long-term decline occurred under conditions of historically limited fluoride exposure during childhood [9,10,11], distinguishing it from many other high-income countries.
Japan’s caries decline therefore constitutes a natural social experiment occurring outside fluoride-centered public health interventions traditionally viewed as indispensable. This analysis synthesizes long-term national surveillance data to re-examine Japan’s trajectory in relation to cumulative changes in diet, early-life environments, health-system accessibility, and broader social conditions. These insights are particularly relevant for countries where dental caries remains a substantial health burden or where caries levels are increasing.
In this context, Japan represents a unique and underexplored case. Rather than challenging the established preventive role of fluoride, Japan’s experience extends existing frameworks by demonstrating that population-level caries decline can reach historically unprecedented lows through multicausal pathways. This study therefore focuses on previously overlooked evidence of long-term caries reduction under conditions of limited fluoride exposure, offering insights for settings in which fluoride-based interventions alone have proven insufficient to eliminate disease burden.
Methods
Data sources
National caries trends among 12-year-olds were obtained from the annual School Dental Health Survey conducted by the Ministry of Education, which provides mean DMFT and the proportion of children with DMFT >1 from the 1950s onward [5]. Schools included in the survey are selected based on a stratified sampling framework for reporting, which does not explicitly incorporate geographic factors such as urban and rural location. To corroborate long-term trends and ensure diagnostic consistency, the National Survey of Dental Diseases was consulted, conducted approximately every six years by the Ministry of Health, Labour and Welfare with examination performed by calibrated dentists [6].
Historical U.S. fluoride–DMFT data were taken from Dean [9, 10] and McClure [11], which report community-level mean DMFT across a range of naturally occurring fluoride concentrations.
To contextualize environmental changes, national sugar-availability statistics were obtained from ALIC [7, 12].
Measures
Caries experience was assessed using the permanent-tooth DMFT index and the prevalence of DMFT >1. Japan’s national mean DMFT in 2023 [5] was used as the contemporary reference point for comparison with historical U.S. data [9,10,11].
Analytical approach
National trends were summarized descriptively using time-series plots of mean DMFT and caries prevalence.
Dean’s fluoride–DMFT curve was reconstructed using a third-order polynomial regression fitted to the 27-community dataset [9,10,11]. Japan’s 2023 DMFT value was plotted at an assumed drinking-water fluoride concentration of approximately 0 ppm and compared visually with Dean’s historical minimum.
Sugar availability data from 1980 onward were obtained from the annual supply statistics published by ALIC [12]. Earlier values (1960–1975) were extracted from the figure published by Miyazaki and Morimoto [7], which itself was based on national sugar statistics compiled by the Japan Sugar Refiners Association. Values were digitized visually with an estimated precision of ± 0.2 kg.
Study design considerations
This is an ecological synthesis of national surveillance data and historical datasets; no formal causal inference was attempted.
The purpose was to reinterpret long-term national trends and situate Japan within the historical fluoride–DMFT framework.
Results
Forty years of continuous decline
Figure 1 shows Japan’s national caries trends among 12-year-olds, the global standard indicator for monitoring permanent-tooth caries. Gray dots represent the percentage of children with > 1 decayed, missing, or filled permanent tooth (DMFT > 1), whereas black dots connected by a solid line represent the national mean DMFT index.
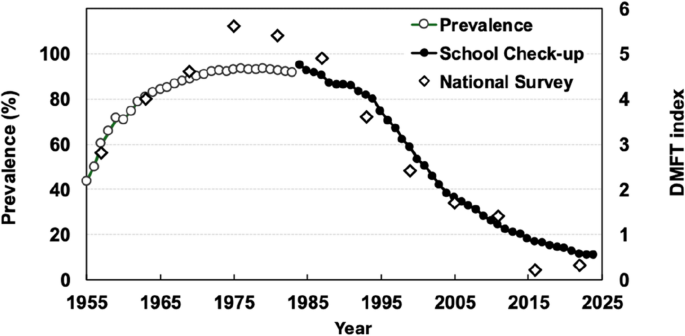
Dental caries trends among 12-year-olds in Japan, 1950–2023. Gray dots show the proportion of children with > 1 decayed, missing, or filled permanent tooth (DMFT > 1), based on national school dental health surveys. Black dots connected by a solid line show the national mean DMFT index
Although the School Health Statistics are based on a stratified sampling framework for reporting, the underlying school dental examinations are conducted routinely for nearly all children nationwide, and the sampling design has remained stable over time, ensuring high representativeness and comparability of long-term trends. Indeed, caries experience rose steadily from the 1950s through the early 1980s, when more than 90% of children were affected. Among those with caries, the mean DMFT was 4.75 in 1984 [5]. Thereafter, Japan experienced a remarkably smooth and continuous decline. Mean DMFT fell below 1.0 after 2015 [5] and reached 0.53 in 2023, with no evidence of reversal or plateau at any point across four decades. This downward trajectory contrasts with trends in several countries, where caries reduction slowed or stalled in the 2000s [1].
Decline occurred without universal fluoride exposure
During this same 40-year period, Japan had no community water fluoridation, and the most widely recommended children’s toothpastes contained 500 ppm fluoride—a concentration shown in systematic reviews to provide only limited caries-preventive effects in early childhood [13, 14]. High-fluoride toothpaste (1,500 ppm) became widely accessible only after 2017 [8], and had not been recommended for children under 14 years of age until 2023—a point well after Japan’s major decline had already occurred. This timeline indicates that Japan’s long-term caries reduction cannot be attributed to population-wide use of high-fluoride toothpaste. For most of the four decades during which caries declined continuously, children used only low-fluoride formulations (< 1,000 ppm). Thus, although fluoride toothpaste contributes to contemporary caries control, it cannot explain the historical downward trend observed in Japan [5, 6]. These patterns indicate that Japan’s long-term decline cannot be attributed to population-wide fluoride exposure and invite comparison with historical fluoride–DMFT benchmarks [9,10,11].
Japan’s present caries level lies far below the minimum DMFT observed in Dean’s dataset
Japan’s current national caries level lies well below the minimum DMFT values historically reported by Dean in high-fluoride communities. A notable contrast emerges when Japan’s present-day caries levels are compared with the classic U.S. ecological studies by Dean [9, 10] and later consolidated by McClure [11]. The 27-community dataset—long used to justify the “optimal fluoride concentration” of 0.7–1.2 ppm—showed that mean DMFT rarely fell below 2, even in high-fluoride communities with naturally occurring concentrations of 2–3 ppm [9,10,11]. Japan’s national mean DMFT of 0.53 in 2023 [5] is therefore far lower than the minimum values observed in these high-fluoride settings, suggesting that substantial population-level caries reductions can occur even without water fluoridation when broader social, behavioral, and environmental determinants improve.
Figure 2 compares Japan’s 2023 national DMFT with the historical relationship originally documented by Dean in the 1930s–1940s [9, 19]. These data—later consolidated by McClure in Fluoride Drinking Water in the United States (1962) [11]—formed the empirical basis for defining the “optimal” fluoride concentration in North American policy.
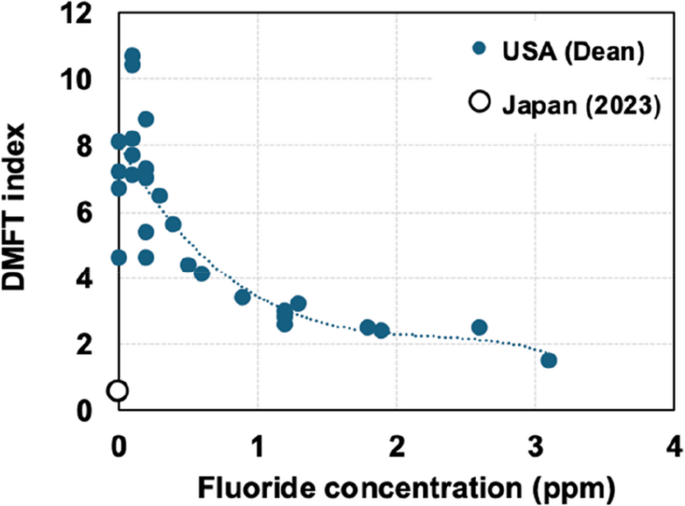
Relationship between fluoride concentration in drinking water and dental caries (Dean dataset plus Japan, 2023). Scatter points show Dean’s historical data on the association between natural fluoride concentrations in drinking water and mean DMFT among U.S. children (1930–1940s). The solid curve represents a third-order polynomial regression fitted to Dean’s original data. The red point indicates the national mean DMFT of Japanese 12-year-olds in 2023 (DMFT = 0.53), plotted for reference. The figure illustrates that Japan’s current caries level is substantially lower than the minimum DMFT observed in Dean’s dataset, even at fluoride concentrations around 2 ppm
In contrast, Japan’s current DMFT lies well below the lowest value reported in Dean’s findings, despite Japan’s drinking-water fluoride concentration being effectively 0 ppm. This divergence indicates that the apparent “biological minimum” observed in the Dean era reflected the environmental and social conditions of the time rather than a true physiological limit.
Japan’s trajectory demonstrates that population-level caries experience can fall substantially below the historically fluoride-associated minimum, even without community water fluoridation and without early widespread availability of high-fluoride toothpaste [5].
Sugar consumption decreased markedly
Figure S1 shows that Japan’s annual per-capita sugar consumption decreased by over 30% since its peak around 1975 [7, 12]. Unlike many countries during the same period, where sugar intake rose or plateaued, Japan experienced a sustained secular decline in sugar exposure—one of the strongest known population-level determinants of dental caries [15,16,17,18].
Discussion
The findings of this study call for a re-examination of how long-term population-level caries decline is conceptualized within broader population health and social epidemiological frameworks. Seminal ecological studies by Dean established a foundational relationship between fluoride exposure and reductions in dental caries, forming the scientific basis for decades of global caries prevention policy. Japan’s experience does not challenge the established preventive role of fluoride, but extends this framework by demonstrating that sustained caries decline can continue—and reach historically unprecedented lows—even under conditions of limited fluoride exposure.
Rather than resulting from a single dominant intervention, Japan’s four-decade decline appears to reflect the cumulative and synergistic effects of multiple modest changes in diet, early-life environments, health-system accessibility, and broader social conditions. Viewed in this light, Japan represents a large-scale natural social experiment that complements, rather than contradicts, fluoride-centered prevention models, highlighting additional pathways through which population-level gains can be achieved.
Changes in dietary patterns
Reductions in sugar intake—particularly from beverages and processed foods—likely played an important contributory role in Japan’s caries decline. Ecological associations between sugar availability and DMFT have been documented repeatedly across countries and historical contexts [15,16,17,18]. In Japan, national supply statistics indicate a gradual decline in per-capita sugar availability beginning in the mid-1970s [7, 12], temporally coinciding with the early phase of caries reduction. This decline may reflect broader societal changes, including shifts in dietary habits, reduced consumption of sugar-sweetened beverages, and increased public awareness of health.
These observations are consistent with earlier interpretations by Miyazaki and Morimoto [7], who emphasized the role of declining national sugar consumption during the 1970s and early 1980s in Japan’s subsequent reduction in dental caries. However, although reductions in sugar intake were clearly influential, the continued and remarkably smooth decline in DMFT long after sugar availability stabilized suggests that dietary change alone cannot account for Japan’s four-decade trajectory.
Changes in early childhood feeding and parenting practices
Changes in early childhood feeding and caregiving practices may also have contributed to Japan’s long-term decline in dental caries. A substantial body of evidence indicates that parent-to-child transmission of mutans streptococci (MS) plays a critical role in shaping early-life microbial colonization and subsequent caries risk trajectories [19, 20]. Reductions in prolonged bottle-feeding, shifts in weaning practices, and increased parental supervision during early childhood are therefore plausible pathways through which population-level caries risk may be modified.
Direct evidence linking caregiver-to-child MS transmission to national caries trends in Japan remains limited. However, Japanese epidemiological studies have documented parallel declines in early childhood caries prevalence and MS infection rates [21], suggesting that early-life oral microbial environments have become less cariogenic over time. Although these studies do not directly observe transmission pathways, they are consistent with a broader body of evidence linking early microbial colonization to later caries risk.
In addition, Japan is characterized by exceptionally high coverage of routine dental health examinations during infancy and early childhood, providing repeated opportunities for caregiver education, early risk awareness, and guidance on feeding and oral hygiene practices. Taken together, these institutional and behavioral changes may have indirectly contributed to more favorable early oral environments, acting cumulatively alongside dietary, health-system, and broader social changes.
Dental access and disease management within the health-care system
Although Japan’s universal health insurance system is not explicitly designed to deliver primary caries prevention, it substantially reduced financial and logistical barriers to accessing dental care across the life course. In practice, this system facilitates early and regular dental attendance and covers the management of suspected carious lesions, gingival inflammation, and related oral hygiene care.
There is no evidence that such system-level accessibility has directly reduced the biological initiation of dental caries. However, by addressing suspected carious lesions and gingival inflammation, dental care encounters often involve oral hygiene instruction and reinforcement of plaque control practices. These interactions may have contributed to improvements in oral hygiene conditions that are closely linked to established determinants of caries risk.
When combined with Japan’s long-standing school dental check-up programs, this environment likely supported more stable caries trajectories by reinforcing early detection, care-seeking behavior, and oral health awareness. In addition, school dental health activities conducted by school dentists may have contributed to sustained improvements in oral health literacy, hygiene awareness, and preventive behaviors among children and families. Although the independent effect of these activities is difficult to quantify, their long-term integration into the educational environment may have reinforced cumulative behavioral and social pathways associated with caries decline. Rather than functioning as a standalone preventive intervention, the insurance-based dental care system may therefore have acted synergistically with dietary changes, early-life caregiving practices, and broader social shifts [22, 23] to sustain Japan’s long-term population-level decline in caries.
Fluoride toothpaste contributed, but at modest strength
Fluoride-containing toothpaste has well-established caries-preventive effects, and its widespread use in Japan likely contributed to caries control to some extent. However, for much of the period during which Japan’s national caries decline occurred, toothpaste formulations available on the market contained substantially lower fluoride concentrations than those currently recommended internationally.
High-fluoride toothpastes (> 1450 ppm), which have been shown in systematic reviews to provide stronger caries-preventive effects [13, 14], were not approved in Japan until 2017 [8] and were not recommended for children of school age until 2023. Prior to 2017, most commercially available toothpastes in Japan contained less than 1000 ppm fluoride, indicating that low-fluoride formulations predominated throughout nearly the entire period of national caries decline.
Market data further suggest that even these lower-fluoride products did not exceed a 90% market share until the early 2000s, implying that widespread population coverage of fluoride toothpaste was achieved relatively late. Consequently, the major phase of Japan’s long-term caries decline unfolded under conditions of limited fluoride exposure from toothpaste. This temporal mismatch indicates that fluoride toothpaste alone cannot account for the observed population-level decline.
Overall, Japan’s experience suggests that population-level caries outcomes are highly modifiable through cumulative environmental, social, and behavioral changes, even under conditions of suboptimal fluoride exposure. At the same time, these influences likely acted synergistically with—rather than in place of—fluoride-based measures.
Policy implications for fluoridated and non-fluoridated settings
Japan’s long-term decline in childhood caries has important implications for oral health policy globally, where countries face wide heterogeneity in caries burden, health-system capacity [1, 4], and the feasibility of population-wide fluoride interventions. For settings in which community water fluoridation is technically, politically, or socially infeasible [3, 4], Japan’s experience demonstrates that substantial and sustained reductions in caries can still be achieved through alternative pathways.
Several Nordic countries have also achieved major reductions in dental caries without community water fluoridation [24,25,26,27], supported by early adoption of high-fluoride toothpaste, comprehensive school dental services, and strong preventive infrastructures. These well-documented experiences show that fluoridation is not a prerequisite for national-level improvement.
The major phase of Japan’s 40-year decline, however, unfolded in the absence of not only community water fluoridation, but also widespread exposure to high-fluoride toothpaste among children of school age, as outlined earlier. Consequently, Japan’s decline occurred under conditions of comparatively limited fluoride exposure from both water [9,10,11] and toothpaste [13, 14], distinguishing it from other non-fluoridated high-income countries.
In addition, topical fluoride applications in Japan are not systematically incorporated into routine school dental check-up programs and are typically provided on an individual basis during dental visits. Although detailed national data on their population-level use are limited, the latest National Survey of Dental Diseases (2024) reported that the experience rates of topical fluoride application, fluoride mouth rinsing, and use of fluoride toothpaste were 58.0%, 28.8%, and 73.1%, respectively, among children aged 10–14 years [6]. These findings suggest that fluoride exposure at the individual level is relatively common; however, their contribution to the long-term national decline in caries remains difficult to quantify and is unlikely to fully account for the observed population-level trends.
This unique combination positions Japan as a distinct natural social experiment, in which multiple non-fluoride pathways—including changes in diet, early-life environments, health-care access, and broader social conditions—converged to produce sustained population-level gains.
Importantly, these gains were achieved at national scale, in a population exceeding 120 million people, and documented through long-standing, standardized school dental examinations with exceptionally high coverage and temporal stability [5]. Such a combination of population size, surveillance continuity, and duration is rare and highly informative globally.
For countries with long-standing fluoride-based prevention strategies [1, 3, 4], Japan’s experience does not argue against fluoride use. Rather, it suggests that further reductions—particularly in settings where inequalities persist—may increasingly depend on complementary strategies addressing diet, early-life conditions, and health-system accessibility, alongside fluoride-based measures.
These likely include changes in parenting practices, earlier and more regular dental attendance, improved management of carious lesions within Japan’s universal health insurance system, and broader social and environmental determinants of health. At the same time, it is likely that additional contributory factors—some of which have yet to be fully elucidated—also played a role in shaping Japan’s long-term caries trajectory. Taken together, these observations suggest that Japan’s sustained population-level caries reduction is best explained by the cumulative and synergistic effects of multiple modest improvements, rather than by any single dominant factor.
In recent years, renewed attention has been directed toward the population-level safety of fluoride exposure, including findings from the U.S. National Toxicology Program (2024) [28], which reported associations between higher levels of fluoride exposure and adverse neurodevelopmental outcomes. However, these findings are primarily derived from studies conducted in areas with elevated natural fluoride levels and may not be directly generalizable to settings with regulated fluoride exposure. In addition, recent studies, including longitudinal and meta-analytic evidence, have reported no clear association between low-level fluoride exposure and cognitive outcomes [29,30,31]. While this body of evidence does not establish a clear threshold nor directly address caries prevention policy, it has contributed to broader discussions regarding the balance between benefit, safety, and equity in fluoride-based interventions.
From a public health perspective, Japan’s experience raises a broader question regarding the continued reliance on population-wide systemic interventions for caries prevention in settings where disease levels have already declined to historically low ranges.
In this evolving public health context, Japan’s long-term experience offers timely and policy-relevant evidence. The present analysis demonstrates that sustained and historically unprecedented reductions in childhood caries can be achieved through cumulative, non-fluoride pathways under conditions of limited systemic fluoride exposure. These findings suggest that effective caries prevention may be attainable through alternative strategies that impose lower financial and social burdens at the population level.
However, these findings should be interpreted within the specific social and health-system context of Japan and should not be directly generalized to settings where such conditions are not present. In particular, this study does not suggest that established fluoride-based interventions should be discontinued where they are effective, but rather highlights the potential importance of complementary population-level strategies.
Conclusion
From a population health perspective, Japan’s experience illustrates how sustained improvements in social, behavioral, and environmental conditions can collectively reshape disease trajectories at national scale. Japan’s 40-year reduction in childhood dental caries—achieved without population water fluoridation and largely preceding widespread access to high-fluoride toothpaste—represents one of the most compelling natural social experiments in modern dental public health.
Importantly, Japan’s current national DMFT level lies far below the minimum values historically observed in the high-fluoride communities documented by Dean. This divergence indicates that environmental, social, and behavioral improvements can lower population-level caries experience beyond thresholds traditionally attributed to fluoride exposure alone.
Japan’s trajectory demonstrates that substantial and sustained reductions in dental caries can be achieved through multicausal pathways, even in the absence of universal water fluoridation. For countries across the world—where caries burden remains high and preventive strategies must operate under diverse constraints—Japan’s experience underscores the value of broad, integrated approaches addressing diet, early-life environments, and access to care alongside fluoride-based measures.
This analysis highlights insights that have long remained unrecognized—not because the evidence was unavailable, but because prevailing frameworks shaped what researchers expected to see.
Data availability
All data analyzed in this study are derived from publicly available sources. National data on dental caries experience among 12-year-olds were obtained from the School Health Statistics Survey conducted by the Ministry of Education, Culture, Sports, Science and Technology (MEXT), Japan (https://www.mext.go.jp).Historical information on fluoride exposure and caries levels was obtained from published literature, including McClure FJ. *Fluoride Drinking Waters* (U.S. Public Health Service, 1962). Data on sugar availability were derived from national food supply statistics published by the Ministry of Agriculture, Forestry and Fisheries (MAFF), Japan (https://www.maff.go.jp).No new datasets were generated or analyzed for this study. All data sources are cited within the manuscript.
References
-
Peres MA, Macpherson LMD, Weyant RJ, et al. Oral diseases: a global public health challenge. Lancet. 2019;394(10194):249–60. https://doi.org/10.1016/S0140-6736(19)31146-8.
-
WHO. Fluoride in Drinking-water. Geneva: World Health Organization. 2004. Available at: https://www.who.int/publications/i/item/fluoride-in-drinking-water (Accessed 8 December 2025).
-
Centers for Disease Control and Prevention. Achievements in public health, 1900–1999: Fluoridation of drinking water to prevent dental caries. MMWR Morb Mortal Wkly Rep. 1999;48(41):933–40.
-
Petersen PE, The World Oral Health Report. 2003. Geneva: World Health Organization; 2003. Available at: https://www.who.int/publications/i/item/world-oral-health-report-2003 (Accessed 8 December 2025).
-
Ministry of Education, Culture, Sports, Science and Technology (Japan). School Dental Health Survey, 1951–2023, Tokyo. MEXT; 2024. Data obtained from the e-Stat government statistics portal. Available at: https://www.e-stat.go.jp/stat-search/files?toukei=00400002&tstat=000001011648 (accessed 8 December 2025). Note: Earlier years prior to 1951 were sex-disaggregated and therefore excluded.
-
Ministry of Health, Labour and Welfare (Japan). National Survey of Dental Diseases, 1957–2024, Tokyo. MHLW; 2024. Data sources: 1957–1993 (original printed reports); 1999–2024 (MHLW online archive). Available at: https://www.mhlw.go.jp/toukei/list/62-17b.html (accessed 3 May 2026).
-
Miyazaki H, Morimoto M. Changes in caries prevalence in Japan. Eur J Oral Sci. 1996;104:452–8. https://doi.org/10.1111/j.1600-0722.1996.tb00112.x.
-
Ministry of Health, Labour and Welfare (Japan). Notification on precautions for the use of high-fluoride dentifrices (up to 1500 ppm). Pharmaceutical and Food Safety Bureau Notification No. 0317-1; 17 March 2017. Available at: https://www.mhlw.go.jp/web/t_doc?dataId=00tc2506&dataType=1 (accessed 8 December 2025).
-
Dean HT, Arnold FA Jr, Elvove E. Domestic water and dental caries. Public Health Rep. 1942;57(32):1155–79.
-
Dean HT, Jay P, Arnold FA Jr, Elvove E. Domestic water and dental caries. Public Health Rep. 1941;56(33):1443–53.
-
McClure FJ. Fluoride Drinking Waters. Washington, DC: U.S. Public Health Service; 1962.
-
Agriculture, Livestock Industries Corporation (ALIC). &. Sugar supply and demand statistics, 1980–2025. Tokyo: ALIC; 2025. Available at: https://sugar.alic.go.jp/japan/data/jd1-1.pdf (Accessed 8 December 2025).
-
Marinho VCC, Higgins JPT, Logan S, Sheiham A. Fluoride toothpastes for preventing dental caries in children and adolescents. Cochrane Database Syst Rev. 2003;1CD002278. https://doi.org/10.1002/14651858.CD002278.
-
Walsh T, Worthington HV, Glenny AM, Appelbe P, Marinho VCC, Shi X. Fluoride toothpastes of different concentrations for preventing dental caries. Cochrane Database Syst Rev. 2019;3:CD007868. https://doi.org/10.1002/14651858.CD007868.pub3.
-
Sheiham A, James WPT. A reappraisal of the quantitative relationship between sugar intake and dental caries. BMC Public Health. 2014;14:863. https://doi.org/10.1186/1471-2458-14-863.
-
Moynihan P, Kelly SA. Effect on caries of restricting sugars intake: a systematic review. J Dent Res. 2014;93(1):8–18. https://doi.org/10.1177/0022034513508954.
-
World Health Organization. Guideline: Sugars Intake for Adults and Children. Geneva: WHO. 2015. Available at: https://www.who.int/publications/i/item/9789241549028 (Accessed 8 December 2025).
-
Sheiham A. Dietary effects on dental diseases. Public Health Nutr. 2001;4(2B):569–91. https://doi.org/10.1079/phn2001142.
-
Köhler B, Andréen I. Mutans streptococci and caries prevalence in children after early maternal infection: a follow-up at 19 years of age. Caries Res. 2012;46(5):474–80. https://doi.org/10.1159/000339665.
-
Berkowitz RJ. Mutans streptococci: acquisition and transmission. Pediatr Dent. 2006;28(2):106–9.
-
Seki M, Yamashita Y. Decreasing caries and mutans streptococci infection. Int Dent J. 2005;55:100–4. https://doi.org/10.1111/j.1875-595x.2005.tb00041.x.
-
Fisher-Owens SA, Gansky SA, Platt LJ, et al. Influences on children’s oral health: a conceptual model. Pediatrics. 2007;120(3):e510–20. https://doi.org/10.1542/peds.2006-3084.
-
Watt RG, Sheiham A. Integrating the common risk factor approach into a social determinants framework. Community Dent Oral Epidemiol. 2012;40(4):289–96. https://doi.org/10.1111/j.1600-0528.2012.00680.x.
-
World Health Organization. Global oral health status report: towards universal health coverage for oral health by 2030. Geneva: WHO; 2022.
-
OECD. Health at a Glance 2023: OECD Indicators. Paris: OECD Publishing; 2023.
-
Källestål C, Wang NJ, Petersen PE, Arnadottir IB. Caries-preventive methods used for children and adolescents in Denmark, Iceland, Norway and Sweden. Community Dent Oral Epidemiol. 1999;27(2):144–51. https://doi.org/10.1111/j.1600-0528.1999.tb02004.x.
-
Christensen LB, Petersen PE, Hede B. Oral health in children in Denmark under different public dental health care schemes. Community Dent Health. 2010;27(2):94–101.
-
National Toxicology Program. NTP monograph on the state of the science concerning fluoride exposure and neurodevelopment and cognition: a systematic review. NTP Monogr. 2024;8:NTP–MGRAPH. https://doi.org/10.22427/NTP-MGRAPH-8.
-
Do LG, Sawyer A, John Spencer A, et al. Early Childhood Exposures to Fluorides and Cognitive Neurodevelopment: A Population-Based Longitudinal Study. J Dent Res. 2025;104(3):243-250. https://doi.org/10.1177/00220345241299352.
-
Kumar JV, Moss ME, Liu H, Fisher-Owens S. Association between low fluoride exposure and children’s intelligence: a meta-analysis relevant to community water fluoridation. Public Health. 2023;219:73-84 https://doi.org/10.1016/j.puhe.2023.03.011.
-
Warren JR, Rumore G, Kim S, et al. Childhood fluoride exposure and cognition across the life course. Sci Adv. 2025;11(47):eadz0757. https://doi.org/10.1126/sciadv.adz0757.
Acknowledgements
The author acknowledges the use of ChatGPT (OpenAI) for assistance with language editing and clarity of expression. The author reviewed and edited the content as needed and takes full responsibility for the accuracy, interpretation, and integrity of the final manuscript.
Funding
This research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
Ethics declarations
Ethics approval and consent to participate
This study was based exclusively on the analysis of aggregated, publicly available national surveillance data and did not involve individual-level data or human participants. Therefore, ethical approval and informed consent were not required.
Consent for publication
Not applicable.
Competing interests
The authors declare no competing interests.
Supplementary Information