
Research Studies
Study Tracker
Prenatal fluoride exposure and pregnancy outcomes in two US pregnancy cohorts.
Abstract
Original full-text study online at
https://academic.oup.com/ije/article/55/5/dyag177/8768834
Background
Our goal was to evaluate the relationship between prenatal fluoride exposure and pregnancy outcomes.
Methods
We measured urinary fluoride collected during the second trimester among pregnant people recruited from California and Illinois from 2014 to 2020 (N = 949). We evaluated risk differences (RDs) of preterm birth (PTB), small-for-gestational age (SGA), large-for-gestational age (LGA), gestational diabetes, and differences in birthweight, birthweight-for-gestational age z-scores, and gestational age associated with a 0.1 mg/l increase in fluoride using linear regression to estimate effects on the additive scale. We also used modified treatment policies with machine learning to estimate the effects of hypothetical interventions to reduce urinary fluoride by 0.1 and 0.5 mg/l on pregnancy outcomes. In the Illinois cohort, we estimated effects by trimester.
Results
In our main analyses, we found no associations between urinary fluoride levels and pregnancy outcomes. For instance, for a 0.1 mg/l increase in fluoride, we saw no change in the risk of PTB, SGA, or gestational diabetes. We also found no differences associated with hypothetical reductions of prenatal fluoride by 0.1 mg/l or 0.5 mg/l for any outcomes. In the trimester-specific analyses for Illinois participants, we found increased LGA risk during the first (RD = 0.004, 95% CI -0.001, 0.009) and third trimesters (RD = 0.007, 95% CI 0.001, 0.012), and reduced LGA risk during the second trimester (RD = 0.006, 95% CI -0.011, 0.000), associated with 0.1 mg/l higher urinary fluoride.
Conclusions
Prenatal fluoride exposure does not appear to affect pregnancy outcomes, but preliminary evidence suggests that higher fluoride levels may affect the risk of LGA depending on timing of exposure during pregnancy.
Key Messages
-
We hypothesized that prenatal fluoride exposure is associated with gestational diabetes, preterm birth, large-for-gestational age, and small-for-gestational age.
-
We did not find associations between fluoride exposure during pregnancy and risk for gestational diabetes or birth outcomes.
-
This lack of association adds important evidence about whether there are health risks of fluoride consumption during pregnancy for birth and pregnancy outcomes.
Introduction
Fluoride has been added to community water supplies to promote dental health in the USA since 1945. Due to increased fluid consumption, pregnant people have been identified as a potentially sensitive subpopulation with respect to fluoride [1], yet the effect of prenatal fluoride exposure on pregnancy outcomes is understudied. Prior studies among pregnant people who lived in areas with fluoridated water show that fetuses are exposed to fluoride in utero from cord blood [2] and amniotic fluid [3, 4], and fluoride consumption in early life can adversely affect neurodevelopment among children [5–7]. Many adverse pregnancy outcomes, like preterm birth (PTB) and small-for-gestational age (SGA), are on the pathway to delayed infant neurodevelopment [8, 9], underscoring the need to assess whether fluoride is associated with pregnancy outcomes.
However, there is limited and conflicting evidence about whether in utero fluoride exposure affects birth outcomes or pregnancy complications. For instance, a study in Sweden found a higher risk of large-for-gestational age (LGA) among pregnant people with higher levels of urinary fluoride [10]. Similarly, a study in California found that higher water fluoride was associated with higher birthweight, increased risk for LGA and fetal macrosomia, although associations were small [11]. In contrast, a study using the US National Health and Nutrition Examination Survey (NHANES), a nationally representative survey of adults and children including interviews and collection of biologic samples, found that higher water fluoride during pregnancy was associated with an increased risk of low birthweight [12]. In India, researchers found 8.7 higher odds of PTB and 10.6 higher odds of low birthweight among mothers with serum fluoride levels >1 ppm [13], and researchers in Senegal found increased risk of low birthweight among mothers with dental fluorosis and those who consumed well water during pregnancy in areas of endemic fluoride contamination [14]. A study in Mexico found differential associations with birthweight depending on the timing of exposure during pregnancy [15]. On the other hand, in Massachusetts, researchers found a protective association of the joint effects of water fluoridation and dental cleaning on risk of PTB [16], while a study in Canada measuring urinary fluoride, fertility, PTB, and SGA did not find any associations [17]. These mixed findings motivate additional research, with greater attention paid to potential mechanisms, dosage, and timing of exposure.
While epidemiologic evidence in the USA is limited, some studies suggest potential mechanisms linking fluoride exposure to adverse pregnancy outcomes. For instance, high levels of fluoride in water have been linked to hypertension [18] and other adverse cardiovascular outcomes [19], which may increase systemic inflammation and oxidative stress, leading to adverse birth outcomes [20, 21]. Fluoride exposure may also disrupt thyroid hormone levels [22–24]. Many other endocrine-disrupting chemicals have been linked to adverse birth outcomes due to the key role of hormones in regulating the normal processes of gestation and parturition [25, 26].
In this study, we evaluated whether prenatal fluoride exposure affects birth outcomes and gestational diabetes in two places where water is fluoridated to the 0.7 mg/l level recommended by the US Public Health Service. We also assessed whether reducing prenatal fluoride exposure would reduce the risk of adverse pregnancy outcomes.
Data and methods
This study used two pregnancy cohorts, the Chemicals in Our Bodies (CiOB) cohort based in the San Francisco Bay Area, California, and the Illinois Kids Development Studies (IKIDS) cohort, based in Champaign-Urbana, Illinois. Both cohorts enrolled pregnant people and collected participant urine during the second trimester.
Chemicals in Our Bodies
Participants were eligible for inclusion in the CiOB cohort if they were English- or Spanish-speaking pregnant people from the prenatal patient population at Chan-Zuckerberg San Francisco General and the Moffitt Long or Mission Bay Hospitals at University of California, San Francisco (UCSF) Mission Bay. Participants had to be at least 18 years old and in their second trimester of pregnancy (between 13 and 27 weeks) to be eligible. Spot urine samples were collected at the second trimester study visit and frozen at -80° Celsius until fluoride measurement.
Illinois Kids Development Study (IKIDS)
Participants were eligible for the IKIDS cohort if they received prenatal care at the Carle Physician Group or Christie Clinic in Champaign-Urbana, Illinois. Participants were recruited at their first prenatal appointment, and first-morning urine was collected from participants during the first, second, and third trimesters. Urine was frozen at -80° Celsius until fluoride measurement. Additional details on CiOB and IKIDS recruitment methods are provided elsewhere [27]. The Institutional Review Boards at the UCSF (10–00861), UC Berkeley (2010–05-04), and University of Illinois (IRB24-0727) approved this study, and all participants provided written, informed consent prior to enrollment.
We included all participants with a urinary fluoride measurement, resulting in a sample size of 949; 598 were from CiOB and 351 from IKIDS.
Fluoride measurement
Urinary fluoride for both cohorts was measured by Ion Selective Electrode (ISE) in the New York State Department of Health, Wadsworth Center’s Laboratory of Inorganic and Nuclear Chemistry. Briefly, an Orion Star A214 meter was used with a Thermo Scientific combination fluoride ion electrode (ThermoFisher Scientific, Waltham, MA). A five-point calibration curve was established with calibration standards diluted from a National Institute of Standards and Technology (NIST)-traceable fluoride standard solution. Urine samples were thawed to room temperature and mixed on a laboratory rocker for 1 hour. After thawing and mixing at room temperature, a 1-ml aliquot of urine was diluted with 1 ml of a total-ionic strength adjustment buffer (TISAB) solution in an 8-ml polypropylene tube and then placed on a lab rocker for 30 minutes to allow for complete mixing. Two concentration levels of urine-based quality control (QC) materials were analyzed with each batch of urine samples as well as a reagent blank. During the analysis, each urine sample was placed on a magnetic stirrer to ensure continued sample mixing. The analysis time was 2 minutes per sample. Wadsworth Center is one of three NIH-funded Human Health Exposure Analysis Resource (HHEAR) laboratory hubs specializing in targeted analysis of biospecimens. The laboratory follows all HHEAR QC protocols. External QC was monitored via satisfactory participation in the proficiency testing (PT) program (PCI) operated by L’Institut National de Santé Publique du Québec (INSP), Centre de Toxicologie du Québec (CTQ), and in the German External Quality Assurance Scheme (G-EQUAS) for trace elements. Bias between the measured (i.e. reported) value and assigned value was < ±15% for all samples. Method precision, expressed as the percent relative standard deviation (%RSD), was estimated using internal QC data and was 4.3% and 2.4% for the low (2.17 mg/l) and high (7.50 mg/l) levels, respectively. The method limit of detection (LOD) was 0.049 mg/l. The method was periodically validated during the study using archived PT samples provided by CTQ.
Pregnancy outcomes
Gestational age at delivery, birthweight, fetal sex, and diagnoses of gestational diabetes were abstracted from the participant medical record. We analyzed gestational age at birth in completed weeks, birthweight in grams, and sex-specific birthweight for gestational age z-scores using a population reference [28]. Each of these was analyzed continuously. We also examined PTB (delivery <37 weeks gestation), SGA, LGA, and gestational diabetes. SGA and LGA were defined as sex-specific birthweight below the 10th percentile and above the 90th percentile, respectively, based on a population reference [28].
Covariates
We controlled for maternal age at delivery, parity, marital status, employment, educational attainment, race/ethnicity, pre-pregnancy BMI, cohort, fetal sex, season of conception, gestational age at sample collection, health insurance type, and urinary specific gravity [29]. Covariates came from the participant medical record and surveys; the source for each variable is listed in the Supplemental Material. The hypothesized data generating mechanism is shown in a directed acyclic graph (DAG) (Supplementary Fig. S1). A simplified DAG limiting to variables included in the analysis is shown in Supplementary Fig. S2. Details on how covariates were classified are provided in the Supplemental Material.
Statistical analysis
To address covariate missingness, we used multiple imputation with 30 imputed datasets. We used Rubin’s combining rules to calculate standard errors [30, 31]. We used linear regression to estimate additive associations for increases in 0.1 mg/l of urinary fluoride in mid-gestation with each of the pregnancy outcomes. We used a linear regression model for both continuous and binary outcomes because we were interested in estimating effects on the additive scale. We evaluated the model residuals to ensure the model fit was appropriate.
We also estimated the effects of hypothetical interventions to reduce urinary fluoride by 0.1 and 0.5 mg/l among those who had urinary fluoride levels above 0.1 or 0.5 mg/l, respectively, on each of our pregnancy outcomes. To do this, we used the modified treatment policies framework [32], which models the effects of hypothetical interventions with continuous exposures using machine learning, and is able to get theoretically-valid inference based on the efficient influence function. This approach allows us to make fewer assumptions about the data-generating distribution, minimize bias due to model misspecification, reduce bias due to positivity violations or extrapolation, and respect the bounds of the outcome distribution. To model the exposure-outcome relationship, we used Super Learner [33], which uses cross-validation to select the combination of algorithms that minimize prediction error. We included the following algorithms in our library: generalized linear models (glm), Bayes glm, big LASSO, glm interaction, and step interaction.
Sensitivity analyses
To evaluate whether we could identify critical windows of exposure to fluoride using the IKIDS cohort, we estimated the effects of a 0.1 mg/l increase in fluoride levels on pregnancy outcomes for exposure during the first, second, and third trimester. Each trimester fluoride and specific gravity level were included in the model to mitigate potential seasonal confounding or correlation between exposures in different trimesters [34]. For comparison with other studies, we also present risk ratios for the binary outcomes.
Results
The CiOB cohort had more participants who were less than age 25 and older than 40 compared to the IKIDS cohort (Table 1). The CiOB cohort was also more likely to be nulliparous, not currently working, have high school education or less, have public health insurance, and be Hispanic/Latina than the IKIDS cohort. The distribution of fluoride levels was similar between the two cohorts, although IKIDS had a slightly higher mean level (0.97 mg/l vs. 0.87 mg/l in CiOB) (Table 2).
Table 1
Descriptive statistics of CiOB and IKIDS study participants.
| CiOB (N = 598) | IKIDS (N = 351) | |
|---|---|---|
| N (%) | N (%) | |
| Maternal age | ||
| Less than 25 | 47 (7.9) | 12 (3.5) |
| 25–less than 30 | 61 (10.2) | 105 (30.0) |
| 30–less than 35 | 238 (39.8) | 170 (48.3) |
| 35–less than 40 | 211 (35.3) | 56 (15.8) |
| 40 or older | 41 (6.9) | 8 (2.3) |
| Parity | ||
| 0 | 310 (51.9) | 80 (22.8) |
| 1 | 174 (29.1) | 190 (54.2) |
| 2 | 80 (13.3) | 58 (16.4) |
| 3 or more | 34 (5.8) | 23 (6.5) |
| Marital status | ||
| Married or living with partner | 551 (92.2) | 342 (97.4) |
| Widowed, separated, or divorced | 7 (1.2) | 1 (0.3) |
| Never married | 40 (6.6) | 8 (2.3) |
| Employment | ||
| Currently working for pay | 455 (76.0) | 303 (86.2) |
| Not currently working for pay | 143 (24.0) | 48 (13.8) |
| Educational attainment | ||
| Less than high school | 53 (8.9) | 0 (0.0) |
| High school or GED | 71 (11.9) | 3 (0.9) |
| Some college or associate’s degree | 60 (10.1) | 44 (12.5) |
| Bachelor’s degree | 157 (26.2) | 130 (37.0) |
| Graduate degree | 257 (43.0) | 174 (49.5) |
| Health insurance type | ||
| Employer-sponsored insurance | 401 (67.1) | 306 (87.2) |
| Public insurance | 187 (31.3) | 24 (6.8) |
| Veteran’s affairs or military insurance | 0.0 | 6 (1.8) |
| Self-purchased insurance | 0.0 | 14 (4.1) |
| Uninsured | 10 (1.7) | 0 (0.0) |
| Race/ethnicity | ||
| White, non-Hispanic | 260 (43.5) | 266 (75.7) |
| Black, non-Hispanic | 25 (4.2) | 12 (3.5) |
| Asian, non-Hispanic | 104 (17.4) | 52 (14.7) |
| Native Hawaiian, other Pacific Islander, American Indian or Alaska Native, or more than one race or other | 33 (5.5) | 11 (3.2) |
| Hispanic/Latina | 176 (29.4) | 10 (2.9) |
| Pre-pregnancy BMI | ||
| Less than 20 | 71 (11.9) | 32 (9.1) |
| 20–less than 25 | 273 (45.6) | 162 (46.3) |
| 25–less than 30 | 146 (24.4) | 79 (22.5) |
| 30–less than 35 | 64 (10.7) | 41 (11.6) |
| 35 or higher | 44 (7.3) | 37 (10.5) |
| Season of conception | ||
| Fall | 145 (24.2) | 95 (27.0) |
| Winter | 161 (26.9) | 80 (22.9) |
| Spring | 140 (23.4) | 93 (26.4) |
| Summer | 152 (25.4) | 83 (23.7) |
| Fetal sex | ||
| Male | 306 (51.2) | 169 (48.1) |
| Female | 292 (48.8) | 182 (51.9) |
| Specific gravity (mean) | 1.015 | 1.016 |
| Gestational age at sample collection (mean, in weeks) | 23.0 | 17.1 |
Numbers within groups may not sum to the total due to rounding from multiple imputation.
Table 2
Distribution of urinary fluoride in mg/l in CiOB and IKIDS participants.
| Min | 25th percentile | 50th percentile | Mean | 75th percentile | Max | |
|---|---|---|---|---|---|---|
| CiOB (N = 598) | 0.09 | 0.51 | 0.72 | 0.87 | 1.12 | 3.42 |
| IKIDS (N = 351) | 0.15 | 0.62 | 0.87 | 0.97 | 1.21 | 3.65 |
| Overall (N = 949) | 0.09 | 0.54 | 0.77 | 0.90 | 1.16 | 3.65 |
We observed null risk differences (RDs) for PTB (RD = 0.002, 95% CI -0.002, 0.005), SGA (RD = 0.001, 95% CI -0.002, 0.004), LGA (RD = 0.002, 95% CI -0.002, 0.006), and gestational diabetes (RD = 0.002, 95% CI -0.002, 0.006) associated with a 0.1 mg/l increase in fluoride levels (Fig. 1). The risk ratio results for these outcomes are shown in Supplementary Table S1. We also found no differences for gestational age (difference in weeks = -0.012, 95% CI -0.037, 0.013), birthweight (difference in grams = 0.13, 95% CI -6.94, 7.20), or birthweight-for-gestational age z-scores (difference = 0.004, 95% CI -0.009, 0.016) (Table 3).
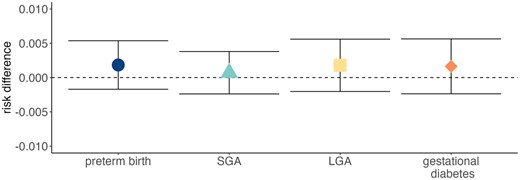
Risk differences and 95% confidence intervals for adverse pregnancy outcomes associated with a 0.1 mg/l increase in urinary fluoride levels (N = 949). These analyses controlled for maternal age at delivery, parity, marital status, employment, educational attainment, race/ethnicity, pre-pregnancy BMI, cohort, fetal sex, season of conception, gestational age at sample collection, health insurance type, and urinary specific gravity.

Table 3
Differences and 95% confidence intervals for birthweight, gestational age, and birthweight-for-gestational age z-scores associated with a 0.1 mg/l increase in urinary fluoride levels, and hypothetical interventions to reduce urinary fluoride levels by 0.1 mg/l or 0.5 mg/l among those with levels above 0.1 or 0.5 mg/l, respectively (N = 949).
| Difference associated with 0.1 mg/l increase in urinary fluoride(95% CI) | Difference associated with a hypothetical intervention to reduce urinary fluoride by 0.1 mg/l | Difference associated with a hypothetical intervention to reduce urinary fluoride by 0.5 mg/l | |
|---|---|---|---|
| (95 % CI) | (95 % CI) | ||
| Birthweight (g) | 0.13 (-6.94, 7.20) | -0.33 (-7.24, 6.58) | 1.05 (-20.64, 22.74) |
| Gestational age (weeks) | -0.012 (-0.037, 0.013) | 0.011 (-0.011, 0.033) | 0.038 (-0.034, 0.110) |
| Birthweight-for-gestational age z-scores | 0.004 (-0.009, 0.016) | -0.004 (-0.015, 0.009) | -0.006 (-0.046, 0.034) |
These analyses controlled for maternal age at delivery, parity, marital status, employment, educational attainment, race/ethnicity, pre-pregnancy BMI, cohort, fetal sex, season of conception, gestational age at sample collection, health insurance type, and urinary specific gravity.
We saw no associations with pregnancy outcomes for the hypothetical interventions to reduce urinary fluoride levels by 0.1 mg/l for those with levels above 0.1 mg/l. For instance, we observed RDs of -0.001 (95% CI -0.004, 0.002) for PTB, 0.000 (95% CI -0.004, 0.004) for SGA, -0.002 (95% CI -0.006, 0.002) for LGA, and -0.002 (95% CI -0.007, 0.004) for gestational diabetes associated with the hypothetical intervention to reduce fluoride by 0.1 mg/l (Fig. 2). We also observed no associations for the continuous measures of perinatal outcomes. For a hypothetical intervention to reduce fluoride by 0.1 mg/l, we observed no effects on gestational age (difference in weeks = 0.011, 95% CI -0.011, 0.033), birthweight (difference in grams = -0.33, 95% CI -7.24, 6.58), or birthweight-for-gestational age z-scores (difference = -0.003, 95% CI -0.015, 0.009) (Table 3). For the hypothetical intervention to reduce prenatal fluoride by 0.5 mg/l, we also observed null effects for PTB (RD = -0.005, 95% CI -0.015, 0.005), SGA (RD = 0.000, 95% CI -0.010, 0.010), LGA (RD = -0.008, 95% CI -0.021, 0.004), or gestational diabetes (RD = -0.003, 95% CI -0.018, 0.011) (Fig. 3). We found no effects for the hypothetical intervention to reduce fluoride by 0.5 mg/l on gestational age (difference in weeks = 0.038, 95% CI -0.034, 0.110), birthweight (difference in grams = 1.05, 95% CI -20.64, 22.74), or birthweight-for-gestational age z-scores (difference = -0.006, 95% CI -0.046, 0.034) (Table 3).
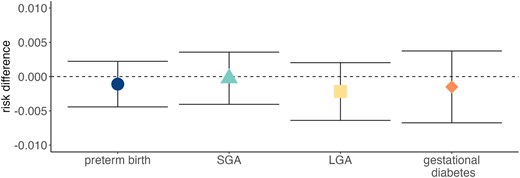
Risk differences and 95% confidence intervals for adverse pregnancy outcomes associated with a hypothetical intervention to reduce urinary fluoride by 0.1 mg/l for those with levels above 0.1 mg/l (N = 949). These analyses controlled for maternal age at delivery, parity, marital status, employment, educational attainment, race/ethnicity, pre-pregnancy BMI, cohort, fetal sex, season of conception, gestational age at sample collection, health insurance type, and urinary specific gravity.

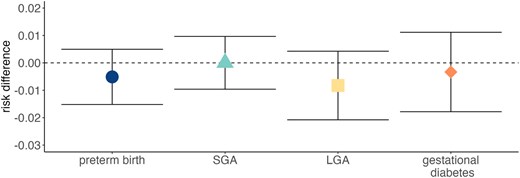
Risk differences and 95% confidence intervals for adverse pregnancy outcomes associated with a hypothetical intervention to reduce urinary fluoride by 0.5 mg/l for those with levels above 0.5 mg/l (N = 949). These analyses controlled for maternal age at delivery, parity, marital status, employment, educational attainment, race/ethnicity, pre-pregnancy BMI, cohort, fetal sex, season of conception, gestational age at sample collection, health insurance type, and urinary specific gravity.

In our trimester-specific analysis in the IKIDS cohort, we found no associations with fluoride on PTB (Supplementary Fig. S3) or birthweight (Table 4). However, we did observe a slight increase in risk of SGA associated with 0.1 mg/l higher fluoride levels during the second trimester (RD = 0.003, 95% CI -0.001, 0.008). We also observed a small increase in risk of gestational diabetes associated with higher urinary fluoride during the third trimester (RD = 0.004, 95% CI -0.002, 0.010). Finally, we observed higher risk of LGA during the first (RD = 0.004, 95% CI -0.001, 0.009) and third trimesters (RD = 0.007, 95% CI 0.001, 0.012) and lower risk during the second trimester (RD = -0.006, 95% CI -0.011, 0.000) associated with 0.1 mg/l higher urinary fluoride levels.
Table 4
Risk differences and 95% confidence intervals for birthweight, gestational age, and birthweight-for-gestational age z-scores associated with a 0.1 mg/l increase in urinary fluoride levels for each trimester of pregnancy among the IKIDS cohort (N = 351).
| First trimester | Second trimester | Third trimester | |
|---|---|---|---|
| (95% CI) | (95% CI) | (95% CI) | |
| Birthweight (g) | -0.43 (-13.89, 13.02) | 3.35 (-11.74, 18.45) | 5.15 (-8.57, 18.88) |
| Gestational age (weeks) | 0.014 (-0.031, 0.058) | -0.005 (-0.055, 0.045) | 0.003 (-0.043, 0.049) |
| Birthweight-for-gestational age z-scores | -0.005 (-0.032, 0.022) | 0.010 (-0.021, 0.040) | 0.013 (-0.015, 0.040) |
These analyses controlled for maternal age at delivery, parity, marital status, employment, educational attainment, race/ethnicity, pre-pregnancy BMI, cohort, fetal sex, season of conception, gestational age at sample collection, health insurance type, and urinary specific gravity.
Discussion
We evaluated whether prenatal fluoride consumption is linked to pregnancy outcomes and estimated the effects of two hypothetical interventions to reduce fluoride exposure. We found no evidence of associations between fluoride and any pregnancy outcome in the main analysis. We also estimated null effects of hypothetical interventions to reduce fluoride consumption on all the pregnancy outcomes we considered. In the analysis limited to the Illinois cohort that had fluoride measured during each trimester, we observed increases in risk of LGA associated with higher fluoride levels during the first and third trimesters, and lower risk of LGA associated with higher fluoride in the second trimester. Fluoride levels were also higher on average in the Illinois compared with the California cohort. These findings suggest that timing and levels of exposure may be important and add important evidence to the discussion around the costs and benefits of fluoride consumption during pregnancy.
There have been several other studies using pregnancy cohorts to estimate effects of urinary fluoride on birth outcomes. A study in Sweden measured urinary fluoride in the late second and early third trimesters, and found higher birthweight (84 g) and odds of LGA (1.39) for a 1 mg/l increase in fluoride levels [10]. The median fluoride level adjusted for specific gravity was 0.86 mg/l, which is similar to the levels in both our cohorts; however, the maximum was 6.4 mg/l which is almost double the maximum in our study. While Sweden does not fluoridate its water, there is natural variation in drinking water fluoride due to local geology. Drinking water fluoride levels in Sweden range from approximately 0 (i.e. non-detectable) to 2 mg/l across districts with an average of 0.35 mg/l [35]. A Canadian pregnancy cohort (with median urinary fluoride levels adjusted for specific gravity of 0.5 mg/l) found no associations between urinary fluoride averaged across pregnancy and birthweight, gestational age, PTB, or SGA [17, 24]. In this study, some participants lived in municipalities with fluoridated drinking water and some did not; the range of drinking water fluoride was 0.04 to 0.87 mg/l. A study in Mexico, where the salt is fluoridated but the water is not, found an increase of 1 mg/l in urinary fluoride in the first trimester for those with high urinary fluoride levels (1 mg/l or higher) was associated with an increase in the birthweight-for-gestational age z-score, while a 1 mg/l increase in urinary fluoride above 0.58 mg/l in the third trimester was associated with lower birthweight [15]. In our analyses of trimester-specific exposures in the IKIDS cohort, we also observed differential effects by trimester. We estimated effects on pregnancy outcomes for a smaller change in urinary fluoride than these prior studies (0.1= mg/l vs. 1 mg/l) because a 1 mg/l increase would represent more than an interquartile range increase in our data, and we had few participants with urinary fluoride levels greater than 1 mg/l. Overall, our work is consistent with several studies that have found null effects of prenatal fluoride on pregnancy outcomes, with heterogeneous findings for fetal growth outcomes depending on timing and level of exposure.
Our study had several limitations. As we recruited participants at prenatal care visits, we may have missed people who experienced early fetal loss. If higher fluoride concentrations were linked to increased risk of fetal loss, our estimates may be biased toward the null [36]. There may be residual confounding between urinary fluoride levels and pregnancy outcomes from dietary factors or co-occurring chemicals in drinking water that we did not measure. We only captured recent fluoride exposure via spot urine samples; fluoride has a half-life of about 5 hours so we could not characterize chronic or cumulative exposures [37]. It is also possible that relationships exist between fluoride consumption and adverse pregnancy outcomes, but we were underpowered in this study to detect their effects. We observed effect modification by trimester among the Illinois cohort, but the California participants only had urine samples collected during the second trimester, leading to a smaller sample size to assess trimester-specific effects.
Our study leveraged detailed pregnancy cohort data, including a linkage of medical records, surveys, and biologic samples for participants in areas where water is fluoridated to the 0.7 mg/l level recommended by the US Public Health Service. We measured urinary fluoride levels collected during mid-gestation and assessed whether higher fluoride levels were associated with birth and pregnancy outcomes. We also evaluated whether hypothetical interventions to reduce fluoride exposure would affect pregnancy outcomes, using doubly-robust estimators that included machine learning to better capture the complex relationships between study variables. In both cases, we did not find evidence of an effect of fluoride. Nevertheless, this study contributes important evidence about the impact of fluoride consumption on reproductive health outcomes. Future work should consider mechanisms underlying the effect modification by trimester on LGA that we observed in this study, as well as the potential for interaction between fluoride and other co-occurring chemicals.
Ethics approval
The Institutional Review Boards at the UCSF (10-00861), UC Berkeley (2010-05-04), and University of Illinois (IRB24-0727) approved this study and all participants provided written, informed consent prior to enrollment.
Acknowledgements
We would like to thank Ms Fida Kased of the Wadsworth Center’s Laboratory of Inorganic and Nuclear Chemistry for technical assistance with the urinary fluoride analyses.
Author contributions
D.E.G. designed the study, acquired funding for the study, wrote the statistical analysis code, conducted the statistical analysis, created the figures and tables, interpreted the results, and wrote and edited the manuscript. S.E.M. helped design the study and interpret the results and edited the manuscript. P.J.P. measured the urinary fluoride concentrations and contributed to interpreting the results and editing the manuscript. A.M.P. helped design the study and interpret the results and edited the manuscript. S.D.G. helped to manage the IKIDS study and contributed to interpreting the results and editing the manuscript. S.L.S. managed the IKIDS study, acquired funding for the measurement of urinary fluoride in the IKIDS study, and contributed to interpreting the results and editing the manuscript. T.J.W. contributed to managing the CiOB study and contributed to interpreting the results and editing the manuscript. R.M.-F. contributed to managing the CiOB study and contributed to designing the study, interpreting the results, and editing the manuscript.
Supplementary material
Supplementary material is available at IJE online.
Conflicts of interest
None declared.
Funding
This work was supported by R00ES033274, P42ES004705 (Superfund Research Program) and UH3 OD023272 from the National Institute of Environmental Health Sciences at the National Institutes of Health.
Data availability
Data are not publicly available due to privacy protections.
Use of artificial intelligence (AI) tools
No AI was used in the preparation of this manuscript.
References
01. National Research Council. Fluoride in Drinking Water: A Scientific Review of EPA’s Standards. Washington, D.C.: The National Academies Press, 2006. https://doi.org/10. 17226/11571
02. Caldera R, Chavinie J, Fermanian J, Tortrat D, Laurent AM. Maternal-fetal transfer of fluoride in pregnant women. Biol Neonate 1988;54:263–9. https://doi.org/10.1159/000242861
03. Abduweli Uyghurturk D, Goin DE, Martinez-Mier EA, Woodruff TJ, DenBesten PK. Maternal and fetal exposures to fluoride during mid-gestation among pregnant women in northern California. Environ Health 2020;19:38. https://doi. org/10.1186/s12940-020-00581-2
04. Ron M, Singer L, Menczel J, Kidroni G. Fluoride concentration in amniotic fluid and fetal cord and maternal plasma. Eur J Obstet Gynecol Reprod Biol 1986;21:213–8. https://doi.org/ 10.1016/0028-2243(86)90018-3
05. Till C, Green R, Flora D et al. Fluoride exposure from infant formula and child IQ in a Canadian birth cohort. Environ Int 2020; 134:105315. https://doi.org/10.1016/j.envint.2019.105315
06. Choi AL, Sun G, Zhang Y, Grandjean P. Developmental fluoride neurotoxicity: a systematic review and meta-analysis. Environ Health Perspect 2012;120:1362–8. https://doi.org/10. 1289/ehp.1104912
07. Taylor KW, Eftim SE, Sibrizzi CA et al. Fluoride exposure and children’s IQ scores: a systematic review and meta-analysis. JAMA Pediatr 2025;179:282–92. https://doi.org/10.1001/jama pediatrics.2024.5542
08. Volpe JJ. Brain injury in premature infants: a complex amalgam of destructive and developmental disturbances. Lancet Neurol 2009;8:110–24. https://doi.org/10.1016/S1474-4422(08) 70294-1
09. Sacchi C, Marino C, Nosarti C, Vieno A, Visentin S, Simonelli A. Association of intrauterine growth restriction and small for gestational age status with childhood cognitive outcomes: a systematic review and meta-analysis. JAMA Pediatr 2020;174: 772–81. https://doi.org/10.1001/jamapediatrics.2020.1097
10. Kampouri M, Gustin K, Stråvik M et al. Association of maternal urinary fluoride concentrations during pregnancy with size at birth and the potential mediation effect by maternal thyroid hormones: the Swedish NICE birth cohort. Environ Res 2022; 214:114129. https://doi.org/10.1016/j.envres.2022.114129
11. Goin DE, Padula AM, Woodruff TJ, Sherris A, Charbonneau K, Morello-Frosch R. Water fluoridation and birth outcomes in California. Environ Health Perspect 2024;132:57004. https:// doi.org/10.1289/EHP13732
12. Arun AK, Rustveld L, Sunny A. Association between water fluoride levels and low birth weight: National Health and Nutrition Examination Survey (NHANES) 2013–2016. Int J Environ Res Public Health 2022;19:8956. https://doi.org/10. 3390/ijerph19158956
13. Sm G, Mohanty S, Vb A, Mishra A, Rao P. Association of higher maternal serum fluoride with adverse fetal outcomes. Int J Med Public Health 2011;1:13–7. https://doi.org/10.5530/ ijmedph.2.2011.4
14. Diouf M, Cisse D, Lo CMM, Ly M, Faye D, Ndiaye O, Pregnant women living in areas of endemic fluorosis in Senegal and low birth weight newborns: case–control study. Revue d’Epidémiologie et de Santé Publique 2012;60:103–8.
15. Ort??z-Garc??a SG, Torres-S?anchez LE, Mu~noz-Rocha TV et al. Maternal urinary fluoride during pregnancy and birth weight and length: results from ELEMENT cohort study. Sci Total Environ 2022;838:156459. https://doi.org/10.1016/j.scitotenv. 2022.156459
16. Zhang X, Lu E, Stone SL, Diop H. Dental cleaning, community water fluoridation and preterm birth, Massachusetts: 2009– 2016. Matern Child Health J 2019;23:451–8. https://doi.org/ 10.1007/s10995-018-2659-y
17. Goodman C, Hall M, Green R et al. Maternal fluoride exposure, fertility and birth outcomes: the MIREC cohort. Environ Adv 2022;7:100135. https://doi.org/10.1016/j.envadv.2021.100135
18. Sun L, Gao Y, Liu H et al. An assessment of the relationship between excess fluoride intake from drinking water and essential hypertension in adults residing in fluoride endemic areas. Sci Total Environ 2013;443:864–9. https://doi.org/10. 1016/j.scitotenv.2012.11.021
19. Liu H, Gao Y, Sun L, Li M, Li B, Sun D. Assessment of relationship on excess fluoride intake from drinking water and carotid atherosclerosis development in adults in fluoride endemic areas, China. Int J Hyg Environ Health 2014;217: 413–20. https://doi.org/10.1016/j.ijheh.2013.08.001
20. Ma Y, Niu R, Sun Z et al. Inflammatory responses induced by fluoride and arsenic at toxic concentration in rabbit aorta. Arch Toxicol 2012;86:849–56. https://doi.org/10.1007/s00204- 012-0803-9
21. Melila M, Rajendran R, Lumo AK et al. Cardiovascular dysfunction and oxidative stress following human contamination by fluoride along with environmental xenobiotics (Cd & Pb) in the phosphate treatment area of Togo, West Africa. J Trace Elem Med Biol 2019;56:13–20. https://doi.org/10.1016/ j.jtemb.2019.07.002
22. Singh N, Verma KG, Verma P, Sidhu GK, Sachdeva S. A comparative study of fluoride ingestion levels, serum thyroid hormone & TSH level derangements, dental fluorosis status among school children from endemic and non-endemic fluorosis areas. Springerplus 2014;3:7. https://doi.org/10.1186/ 2193-1801-3-7
23. Hall M, Hornung R, Chevrier J, Ayotte P, Lanphear B, Till C. Fluoride exposure and thyroid hormone levels in pregnancy: the MIREC cohort. Environ Int 2024;184:108442. https://doi. org/10.1016/j.envint.2024.108442
24. Hall M, Lanphear B, Chevrier J et al. Fluoride exposure and hypothyroidism in a Canadian pregnancy cohort. Sci Total Environ 2023;869:161149. https://doi.org/10.1016/j.scito tenv.2022.161149
25. Zlatnik MG. Endocrine-disrupting chemicals and reproductive health. J Midwifery Womens Health 2016;61:442–55. https://doi.org/10.1111/jmwh.12500
26. Woodruff TJ. Bridging epidemiology and model organisms to increase understanding of endocrine disrupting chemicals and human health effects. J Steroid Biochem Mol Biol 2011; 127:108–17. https://doi.org/10.1016/j.jsbmb.2010.11.007
27.Eick SM, Enright EA, Geiger SD et al. Associations of maternal stress, prenatal exposure to per- and polyfluoroalkyl substances (PFAS), and demographic risk factors with birth outcomes and offspring neurodevelopment: an overview of the ECHO.CA.
8 International Journal of Epidemiology, 2026, Vol, 55, Issue 5
Downloaded from academic.oup.com/ije/article/55/5/dyag177/8768834 by guest on 23 August 2026 IL prospective birth cohorts. Int J Environ Res Public Health 2021;18:742. https://doi.org/10.3390/ijerph18020742
28. Talge NM, Mudd LM, Sikorskii A, Basso O. United States birth weight reference corrected for implausible gestational age estimates. Pediatrics 2014;133:844–53. https://doi.org/10.1542/peds.2013-3285
29. Barr DB, Wilder LC, Caudill SP, Gonzalez AJ, Needham LL, Pirkle JL. Urinary creatinine concentrations in the U.S. population: implications for urinary biologic monitoring measurements. Environ Health Perspect 2005;113:192–200. https:// doi.org/10.1289/ehp.7337
30. Rubin DB. Multiple Imputation for Nonresponse in Surveys. New York, NY: John Wiley & Sons, Inc., 1987.
31. Harel O, Mitchell EM, Perkins NJ et al. Multiple imputation for incomplete data in epidemiologic studies. Am J Epidemiol 2018;187:576–84. https://doi.org/10.1093/aje/kwx349
32. Hoffman KL, Salazar-Barreto D, Williams NT, Rudolph KE, D??az I. Studying continuous, time-varying, and/or complex exposures using longitudinal modified treatment policies. Epidemiology (Fairfax) 2024;35:667–75. https://doi.org/10. 1097/EDE.0000000000001764
33. Laan MJvd, Polley EC, Hubbard AE. Super Learner. Stat Appl Genet Mol Biol 2007;6:1–21. https://doi.org/10.2202/1544- 6115.1309
34. Wilson A, Chiu YHM, Hsu HHL, Wright RO, Wright RJ, Coull BA. Potential for bias when estimating critical windows for air pollution in children’s health. Am J Epidemiol 2017;186: 1281–9. https://doi.org/10.1093/aje/kwx184
35. Aggeborn L, €Ohman M. The effects of fluoride in drinking water. J Polit Econ 2021;129:465–91. https://doi.org/10.1086/71 1915
36. Goin DE, Casey JA, Kioumourtzoglou MA, Cushing LJ, Morello-Frosch R. Environmental hazards, social inequality, and fetal loss: implications of live-birth bias for estimation of disparities in birth outcomes. Environ Epidemiol 2021;5:e131. https://doi.org/10.1097/EE9. 0000000000000131
37. Ekstrand J, Ehrnebo M. The relationship between plasma fluoride, urinary excretion rate and urine fluoride concentration in man. J Occup Med 1983;25:745–8. https://doi.org/10. 1097/00043764-198310000-00014