
Research Studies
Study Tracker
Pulmonary Toxicity and Biodistribution of Sodium Fluoride in Male Rats Following Intratracheal Instillation and Nose-Only Inhalation Exposure.
Abstract
Original full-text study online at
https://www.mdpi.com/2305-6304/14/8/688
fluoride; lung inflammation; biodistribution; hazard; radiotracer
1. Introduction
Chemicals used in household products, which are extensively employed in residential, occupational, and communal settings, pose significant risks to human health and the environment through multiple routes of exposure. The fatalities associated with the use of humidifier disinfectants in Korea have heightened both public awareness and regulatory scrutiny of chemical safety in consumer settings [1,2]. As a result, the safety evaluation of household chemicals has drawn increasing attention, especially for inhalable formulations such as sprays and aerosols. These products have been prioritized in toxicity testing frameworks due to accumulating evidence that highlights severe adverse effects following inhalation exposure [2,3]. The global outbreak of coronavirus disease 2019 (COVID-19) has further accelerated the use of personal hygiene and disinfection products within households, resulting in increased exposure to aerosolized chemical agents [4]. Although these products are effective in controlling microbes, their indiscriminate use can disrupt the ecological balance and, paradoxically, pose risks to human health. These concerns underscore the need for comprehensive toxicological assessments of chemicals used in household products, especially those designed for airborne application.
Among the various chemical agents used domestically, fluoride is of particular interest due to its natural abundance and wide range of applications. Fluoride is the 13th most abundant element in the Earth’s crust, accounting for approximately 0.059% by weight [5]. It is utilized across multiple sectors, including medicine, semiconductor manufacturing, energy materials, optical telecommunications, and liquid crystal technologies. In the medical and public health domains, fluoride is recognized for its cariostatic effects and has been incorporated into community water fluoridation programs in several countries, notably the United States, as a preventive measure against dental caries [6]. However, the widespread application of fluoride has also sparked considerable scientific and public debate due to its associated health risks. Documented adverse effects include dental fluorosis, neurotoxicity, and skeletal malformations, particularly under chronic or excessive exposure conditions [7,8,9]. To mitigate these risks, the World Health Organization has established a guideline limit of 1.5 mg/L for fluoride concentration in drinking water to minimize health risks while preserving its dental benefits [10]. In addition to water supplies, fluoride compounds are commonly found in oral hygiene products, such as toothpaste and mouthwash, with sodium fluoride (NaF) being one of the most widely used agents in these applications [11].
While fluoride in oral care products is primarily intended for dental benefits, it can also cause systemic exposure, not only through ingestion but potentially via mucosal absorption and incidental inhalation during product use or in occupational settings [12,13]. In occupational settings, inhalation exposure to fluoride can occur during manufacturing processes involving fluoride-containing compounds, such as those used in the production of aluminum or semiconductors [12]. To limit such exposure, occupational exposure limits for fluorides (as F) have been established, including a US Occupational Safety and Health Administration (OSHA) permissible exposure limit and a National Institute for Occupational Safety and Health (NIOSH) recommended exposure limit of 2.5 mg/m3 (8-h time-weighted average), consistent with the American Conference of Governmental Industrial Hygienists threshold limit value of the same magnitude [14,15]. Despite these limits, historical workplace monitoring has documented airborne fluoride concentrations of 11–24 mg/m3 among chronically exposed workers, with higher concentrations regarded as elevated [16]. In consumer settings, inhalation exposure can occur through daily activities, such as using fluoride-containing oral care products (e.g., toothpaste and mouthwash) and showering or bathing with fluoridated water. These exposures may occur when fluoride-containing solutions are aerosolized, for example, as fine droplets generated during tooth brushing or mouth rinsing, or when fluoridated water is dispersed through showers, humidifiers, or spray devices. In addition, NaF and other soluble fluorides are incorporated into a range of consumer and industrial products, including certain cleaning agents, wood preservatives, and antimicrobial formulations, some of which may be applied as sprays or aerosols [16]. In contrast to occupational environments, however, airborne NaF concentrations arising from such consumer uses have rarely been quantified. Although inhalation exposure to fluoride is common across various settings, its potential to induce lung inflammation and its biodistribution remain poorly understood. Hence, to address this gap, this study evaluated pulmonary inflammation induced by NaF and related mechanisms using a rat intratracheal instillation model. Additionally, the biodistribution of NaF was evaluated using positron emission tomography/computed tomography (PET/CT) and gamma counting in organs of rats with [18F]NaF as a radiotracer.
2. Materials and Methods
2.1. Preparation of [18F]NaF Radiotracer
2.2. Animal Condition and Care
2.3. Intratracheal Instillation of NaF in Rats to Assess Lung Inflammation
2.4. Bronchoalveolar Lavage Fluid Analysis
2.5. Measurement of Biochemical Parameters and Pro-Inflammatory Cytokines in BALF
2.6. Histological Analysis
2.7. In Vivo Distribution of [18F]NaF in Rats Following Two Different Respiratory Exposures
2.7.1. Inhalation Exposure of [18F]NaF in Rats
2.7.2. Intratracheal Instillation of [18F]NaF in Rats
2.8. PET/CT Imaging of [18F]NaF After Inhalation or Intratracheal Instillation in Rats
2.9. Statistical Analysis
3. Results
3.1. Characteristics of Prepared [18F]NaF

3.2. Acute Lung Inflammation 1 Day After a Single Intratracheal Instillation of NaF


3.3. Lung Inflammation at Days 7 and 28 After a Single Intratracheal Instillation of NaF

3.4. Biodistribution of [18F]NaF After a Single Intratracheal Instillation in Rats

3.5. Biodistribution of [18F]NaF After 1 h Nose-Only Inhalation Exposure in Rats

4. Discussion
NaF is a key component of public health measures, including water fluoridation and oral hygiene products, due to its safety and efficacy [20]. Although humans may inhale NaF through exposure to household products, aerosolized fluoridated water, and occupational settings, the toxicological consequences of inhaled fluoride remain insufficiently characterized. Furthermore, the global increase in the use of personal hygiene aerosols to control microbial contamination underscores the need for a more precise and comprehensive evaluation of their safety in humans and the environment [4]. In this study, we investigated the pulmonary toxicity of NaF to identify potential toxic effects and their related mechanisms. In addition, we evaluated the biodistribution of [18F]NaF using intratracheal instillation and nose-only inhalation models to better understand NaF behavior under two distinct pulmonary exposure scenarios. Importantly, the PET study used tracer-level [18F]NaF for biodistribution analysis, whereas the intratracheal instillation study used mg-level NaF to evaluate toxicological responses. These two approaches were therefore designed to be complementary, with instillation used for hazard identification and inhalation for realistic biodistribution, rather than to define a continuous dose-response relationship; together they provide an integrated view of the pulmonary hazard and systemic fate of inhaled NaF that neither could provide alone.
Several methodological differences between the toxicity and biodistribution experiments warrant clarification, as they were deliberate design choices rather than inconsistencies. First, with respect to the exposure route, the biodistribution of [18F]NaF was characterized by both intratracheal instillation and nose-only inhalation (Figure 5 and Figure 6). The instillation route thus matches the delivery method used in the toxicity study, providing a route-consistent link between the two experiments, while the inhalation route additionally captures the biodistribution under a realistic exposure scenario. The toxicity and biodistribution datasets are therefore not built on mismatched routes. Second, with respect to the dose range, the difference in dose metric is intrinsic to the methods and does not permit, nor did we attempt, a direct numerical comparison. The toxicity study used defined chemical masses of NaF (0.75–3.0 mg/rat) because concentration–response hazard identification requires known chemical doses, whereas the biodistribution study used a no-carrier-added [18F]NaF radiotracer, for which radioactivity (MBq), not chemical mass, is the appropriate dose metric; the negligible chemical mass of the tracer is precisely what allows it to report physiological distribution without perturbing it. Accordingly, the two datasets were interpreted independently on their own dose scales and were never equated. Third, with respect to the sampling time points, the two experiments were designed to resolve processes on different time scales. The toxicity study sampled at days 1, 7, and 28 to track the onset, peak, and resolution of the pulmonary inflammatory response, whereas the biodistribution study sampled over minutes to hours to resolve the rapid absorption, systemic redistribution, and clearance of fluoride. Each sampling schedule was matched to the kinetics of the process being measured, and the delayed inflammatory time course is in fact consistent with, and explained by, the rapid clearance documented in the biodistribution study. Taken together, these design choices make the two experiments complementary and mutually reinforcing rather than contradictory.
Our results demonstrated that NaF induces transient but significant pulmonary inflammation when delivered directly into the lungs. At 24 h post-intratracheal instillation, total BALF cell counts increased in a dose-dependent manner, with marked elevations in neutrophils and eosinophils, alongside increases in LDH and total protein levels, indicating acute cytotoxic injury and increased alveolar–capillary permeability [21,22]. Although the BALF analysis revealed a pronounced inflammatory response, the accompanying histopathological changes were only mild, without destructive tissue damage. This apparent discrepancy reflects the well-recognized difference in sensitivity between the two endpoints rather than a true inconsistency, because BALF analysis is considerably more sensitive than conventional hematoxylin and eosin histopathology for detecting acute pulmonary inflammation. It is also consistent with the rapid pulmonary absorption and clearance of NaF, which limit sustained structural injury after a single exposure. For this reason, the objective and quantitative assessment of pulmonary inflammation is provided primarily by the BALF endpoints; this rationale underlies the 2018 revision of the OECD inhalation toxicity test guidelines (TG 412 and TG 413), which made BALF analysis a mandatory endpoint to complement the more subjective histopathological evaluation [23,24]. Accordingly, semi-quantitative scoring of the near-normal lung tissue would provide little additional discriminatory information beyond the quantitative BALF data.
The eosinophilia observed in BALF may be associated with multiple mechanisms in the lung. One possible explanation is the passive release of intracellular eotaxin from damaged cells, a phenomenon also reported with several nanomaterials, including zinc oxide, copper oxide, and nickel oxide [21,25]. In addition, active secretion by intact epithelial cells in response to inflammatory mediators such as TNF-a may also have contributed to the elevated eotaxin detected in BALF [26]. Previous studies on NaF respiratory toxicity are scarce; however, one report reported neutrophilia without eosinophilia in rats given a single intratracheal instillation of 400 ug/rat NaF, which may have been due to the lower dose used compared with that in the present study [27]. Thus, our findings demonstrate that a single high-dose intratracheal instillation of NaF can induce acute eosinophilic inflammation, potentially exacerbating eosinophil-associated respiratory diseases, highlighting its potential pulmonary hazard. The upstream mechanisms linking NaF exposure to the observed release of TNF-a and eotaxin were not directly investigated in this study, but they can be inferred from the known cellular toxicology of fluoride. In pulmonary cells, NaF increases NADPH oxidase 4 (NOX4)-derived reactive oxygen species, and this oxidative stress activates a p53/death receptor 5 (DR5) axis that drives caspase-mediated apoptosis [28]; fluoride also causes mitochondrial dysfunction that further amplifies reactive oxygen species generation and caspase-dependent cell death [29]. Such oxidative and cytotoxic injury can, in turn, activate downstream inflammatory signaling and promote the release of pre-formed mediators such as eotaxin from damaged cells, consistent with the acute inflammatory response observed here. Nonetheless, the specific upstream pathways (e.g., NOX4/ROS, p53/DR5, and mitochondrial apoptotic cascades) driving NaF-induced pulmonary inflammation were not measured in the present study and warrant dedicated mechanistic investigation in future work.
Although asthma is often driven by antigen-specific allergic sensitization, a non-immunologic form of the disease, termed irritant-induced asthma, can develop when inhaled irritants directly injure the airway epithelium without prior immunological sensitization [30]. The acute, cytotoxicity-driven eosinophilic response observed here is more consistent with such a non-allergic, epithelial injury-driven mechanism, and aerosolized NaF might therefore contribute to eosinophil-associated airway inflammation through direct epithelial cytotoxicity rather than through classical allergic sensitization. Whether repeated exposure sustains this eosinophilic airway inflammation or progresses to chronic pathological changes remains to be determined in repeated-exposure studies. However, intratracheal instillation delivers a bolus dose directly to the lungs, bypassing upper-airway filtration and resulting in substantially higher initial pulmonary deposition than that of realistic inhalation exposure. Therefore, the lung inflammation data in this study should be interpreted primarily as evidence of pulmonary hazard potential rather than as direct risk information for realistic inhalation exposure.
The rapid pulmonary clearance of NaF is not inconsistent with the delayed and sustained inflammatory response. During the brief period when fluoride is absorbed across the pulmonary epithelium, a transient intracellular spike in fluoride concentration is sufficient to trigger cytotoxic injury and induce inflammatory mediators such as TNF-a and eotaxin. Once initiated, this response propagates through a self-amplifying cytokine cascade (for example, TNF-a-driven eotaxin release and eosinophil recruitment) that persists after the triggering agent has been cleared, accounting for the peak of inflammation at day 1 and the elevated eosinophil counts up to day 7. Importantly, this sustained inflammation represents a reversible host response and a process of resolution and repair rather than progressive structural injury, as it was not accompanied by destructive histopathological changes and had fully resolved by day 28. Although repeated pulmonary exposure studies with NaF were not conducted here, repeated oral NaF administration in rats has been shown to cause progressive and irreversible lung alterations, including alveolar septal thickening, fibrosis (collagen deposition), structural remodeling, epithelial hyperplasia, and alveolar damage [31,32]. These findings indicate that the lung may be a target organ of systemic fluorosis and raise the possibility that repeated or chronic inhalation exposure could contribute to similar changes, although this remains a hypothesis that requires confirmation in dedicated inhalation repeated-exposure studies. However, our data also indicate that short-term NaF inhalation is more likely to cause a reversible and tolerable inflammatory response, as all inflammation-related parameters returned to baseline by 28 days post-exposure.
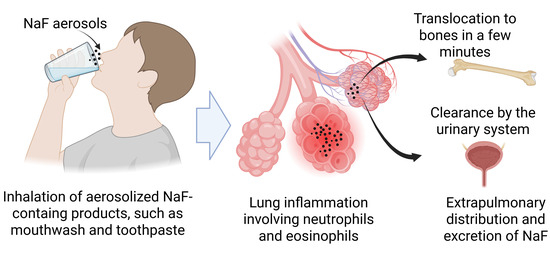
Beyond pulmonary toxicity, we found that [18F]NaF is rapidly absorbed from the lungs and distributed systemically, with preferential skeletal deposition. Following intratracheal instillation, lung uptake of [18F]NaF peaked at 5 min and then rapidly declined, accompanied by progressive accumulation in bone. In contrast, the nose-only inhalation data of [18F]NaF were obtained only after completion of the 1-h exposure period and therefore reflect post-exposure distribution rather than the earliest phase of pulmonary absorption and systemic transfer. Fluoride’s high skeletal affinity is primarily due to ionic substitution of hydroxyl groups in hydroxyapatite to form fluorapatite, which is more stable and acid-resistant [33]. Furthermore, fluoride promotes osteoblastic activity via mitogen-activated protein kinase (MAPK) and Wnt/B-catenin signaling pathways, and suppresses osteoclastic bone resorption by modulating the receptor activator of nuclear factor of kappa-light-chain-enhancer of activated B cells ligand/osteoprotegerin pathway [34]. Importantly, [18F]NaF is a clinically established bone PET tracer in humans, and its documented human biodistribution, characterized by rapid clearance from blood, high first-pass skeletal uptake governed by regional blood flow and bone surface area, and predominant renal and urinary excretion, closely parallels the biodistribution observed here in rats [35]. This concordance supports the physiological relevance of our biodistribution findings to humans and indicates that the lung may serve as an efficient route of systemic fluoride absorption in humans as well. These biodistribution findings are unlikely to be confounded by the isoflurane anesthesia used during the intratracheal procedures. Although isoflurane can be defluorinated to inorganic fluoride, its metabolism is minimal (~0.2%) and increases plasma inorganic fluoride only marginally (on the order of 1 µM) [36]. Furthermore, because [18F]NaF was administered as a no-carrier-added tracer, the skeletal fluoride-binding capacity vastly exceeds the amounts of both the tracer and any isoflurane-derived fluoride, so competition for bone binding sites does not occur, and skeletal tracer uptake is governed by regional blood flow and bone surface area rather than by saturation [35].
This study has several limitations. (1) The intratracheal instillation and nose-only inhalation paradigms had an asymmetric temporal design. Given the rapid absorption and systemic clearance of [18F]NaF, a substantial and unquantified fraction of the inhaled tracer may already have been absorbed, distributed, and partially excreted before the first measurement was taken. Therefore, the inhalation data primarily represent the post-exposure distribution phase and do not capture the full kinetic profile. (2) The inhalation gamma-counter biodistribution analysis was based on a small final sample size (n = 3 per time point), which may have limited sensitivity to detect subtle differences. (3) The aerosol size used in the inhalation study (MMAD: 0.70 µm) and hydrophilicity may have influenced the deposition pattern, with a fraction of inhaled [18F]NaF depositing in the extrathoracic airways rather than the deep lung [37,38]. Material deposited in the nasopharyngeal region could subsequently undergo mucociliary clearance and be swallowed, thereby contributing to the gastrointestinal uptake observed after nose-only inhalation [39]. (4) Pulmonary toxicity was assessed only by intratracheal instillation and not by inhalation. Intratracheal instillation was used because it permits precise control of the delivered pulmonary dose for concentration-response assessment. Evaluation of NaF toxicity under realistic inhalation exposure was beyond the scope of the present study and warrants further investigation in dedicated inhalation toxicity studies. Nevertheless, the two exposure paradigms provide complementary information on [18F]NaF biodistribution under different pulmonary exposure conditions. (5) Only male rats were used in this study because estrogen can modulate pulmonary inflammatory responses [40] and because occupational fluoride exposure has historically predominated in male-dominated settings; consequently, potential sex-specific differences in the pulmonary toxicity and biodistribution of NaF were not evaluated and warrant investigation in future studies including both sexes.
Although fluoride has dental benefits, excessive accumulation in bone, particularly under chronic or repeated exposure, raises concerns about its toxicological effects [41]. PET/CT imaging confirmed time-dependent bone uptake and prominent bladder activity, indicating renal excretion as the primary route of clearance. Additional uptake of [18F]NaF in the GI tract, liver, and kidneys supports mixed excretion pathways, whereas accumulation in soft tissues, such as the heart and brain, was minimal. The high efficiency with which fluoride transits from the pulmonary surface into systemic circulation highlights the lung as a potentially important route of fluoride absorption. This is particularly concerning for aerosolized consumer products, which can lead to repeated low-level exposures in poorly ventilated environments [42]. These findings have important implications for chemical safety evaluation. Current regulatory assessments of fluoride focus largely on ingestion, potentially underestimating inhalation risks. Our results indicate that NaF is efficiently absorbed via the lungs and distributed systemically; therefore, repeated or long-term exposure, even at low doses, may increase the risk of systemic fluoride toxicity, including skeletal accumulation and possible reproductive or neurological effects reported in oral exposure studies [43,44]. This concern is heightened in occupational settings or among individuals who frequently use aerosolized fluoride-containing products [45]. Although this biodistribution study provided valuable information on the systemic fate of inhaled fluoride, the tracer dose used differed from the chemical doses used in the toxicity study, and the effect of dose on the pulmonary and systemic response therefore warrants further study.
The NaF dose used in this study (3 mg/rat, approximately 15 mg/kg) is lower than the total daily occupational exposure limits set by the US OSHA and NIOSH guidelines (i.e., 2.5 mg/m3, 8-h time-weighted average), equivalent to roughly 20 mg/day in humans [14,15]. However, this occupational limit corresponds to ~0.33 mg/kg/day in a 60 kg human, meaning the experimental dose here exceeds typical daily occupational exposure by more than an order of magnitude. Nonetheless, in certain high-risk occupational environments, such as aluminum smelters or phosphate fertilizer plants, airborne fluoride concentrations can significantly exceed OSHA limits, with reported inhalation exposures reaching hundreds of milligrams per day [16]. Thus, the 3 mg/rat dose used here may approximate extreme occupational exposure scenarios. Moreover, the estimated daily fluoride intake from drinking water and toothpaste for the general population (approximately 1–3 mg/day) based on the maximum allowable concentration (4 mg/L) and recommended fluoridation level (0.7 mg/L) of the Environmental Protection Agency (EPA) [46] is comparable to the absolute dose used in our experiment. Because ingested fluoride is systemically absorbed and can accumulate in various organs, including the lungs [16], combined oral and inhalation exposure could produce lung fluoride levels similar to those observed at the 3 mg/rat dose in this study. Therefore, future human health risk assessments should incorporate realistic combined-exposure scenarios to estimate fluoride accumulation and the associated health risks in target organs.
5. Conclusions
The following abbreviations are used in this manuscript:
| NaF | Sodium Fluoride |
| BALF | Bronchoalveolar lavage fluid |
| PET/CT | Positron emission tomography/computed tomography |
| [18F]NaF | Fluorine-18 radiolabeled sodium fluoride |
| COVID-19 | Ccoronavirus disease 2019 |
| QMA | Quaternary methyl ammonium |
| radio-TLC | Radio-thin-layer chromatography |
| KIRAMS | Korea institute of radiological and medical sciences |
| IACUC | Institutional animal care and use committee |
| SD | Sprague-Dawley |
| DW | Distilled water |
| PBS | Phosphate-buffered saline |
| LDH | Lactate dehydrogenase |
| BCA | Bicinchoninic acid |
| IL | Interleukin |
| TNF | Tumor necrosis factor |
| CINC-3 | Cytokine-induced neutrophil chemoattractant-3 |
| ELISA | Enzyme-linked immunosorbent assay |
| 3D-OSEM | 3D ordered subset expectation maximization |
| PMOD | PET model organism database |
| SUV | Standardized uptake value |
| VOI | Volume of interest |
| ANOVA | Analysis of variance |
| GI | Gastrointestinal |
| MMAD | Mass median aerodynamic diameter |
| GSD | Geometric standard deviation |
| OSHA | Occupational safety and health administration |
| NIOSH | National institute for occupational safety and health |
| EPA | Environmental protection Agency |
- Yoon, J.; Kang, M.; Jung, J.; Ju, M.J.; Jeong, S.H.; Yang, W.; Choi, Y.-H. Humidifier Disinfectant Consumption and Humidifier Disinfectant-Associated Lung Injury in South Korea: A Nationwide Population-Based Study. Int. J. Environ. Res. Public Health 2021, 18, 6136. [Google Scholar] [CrossRef] [PubMed]
- Lee, J.-H.; Kim, Y.-H.; Kwon, J.-H. Fatal Misuse of Humidifier Disinfectants in Korea: Importance of Screening Risk Assessment and Implications for Management of Chemicals in Consumer Products. Environ. Sci. Technol. 2012, 46, 2498–2500. [Google Scholar] [CrossRef] [PubMed]
- Larsen, S.T.; Dallot, C.; Larsen, S.W.; Rose, F.; Poulsen, S.S.; Nørgaard, A.W.; Hansen, J.S.; Sørli, J.B.; Nielsen, G.D.; Foged, C. Mechanism of Action of Lung Damage Caused by a Nanofilm Spray Product. Toxicol. Sci. 2014, 140, 436–444. [Google Scholar] [CrossRef] [PubMed][Green Version]
- Dewey, H.M.; Jones, J.M.; Keating, M.R.; Budhathoki-Uprety, J. Increased Use of Disinfectants During the COVID-19 Pandemic and Its Potential Impacts on Health and Safety. ACS Chem. Health Saf. 2022, 29, 27–38. [Google Scholar] [CrossRef]
- Yaroshevsky, A.A. Abundances of chemical elements in the Earth’s crust. Geochem. Int. 2006, 44, 48–55. [Google Scholar] [CrossRef]
- Petersen, P.E.; Lennon, M.A. Effective use of fluorides for the prevention of dental caries in the 21st century: The WHO approach. Community Dent. Oral Epidemiol. 2004, 32, 319–321. [Google Scholar] [CrossRef] [PubMed]
- Choi, A.L.; Sun, G.; Zhang, Y.; Grandjean, P. Developmental Fluoride Neurotoxicity: A Systematic Review and Meta-Analysis. Environ. Health Perspect. 2012, 120, 1362–1368. [Google Scholar] [CrossRef] [PubMed]
- Wei, Y.-L.; Lin, X.-C.; Liu, Y.-Y.; Lei, Y.-Q.; Zhuang, X.-D.; Zhang, H.-T.; Wang, X.-R. Effects of water fluoridation on early embryonic development of zebrafish. Ecotoxicol. Environ. Saf. 2024, 270, 115907. [Google Scholar] [CrossRef] [PubMed]
- Mandinic, Z.; Curcic, M.; Antonijevic, B.; Carevic, M.; Mandic, J.; Djukic-Cosic, D.; Lekic, C.P. Fluoride in drinking water and dental fluorosis. Sci. Total Environ. 2010, 408, 3507–3512. [Google Scholar] [CrossRef] [PubMed]
- Craig, L.; Lutz, A.; Berry, K.A.; Yang, W. Recommendations for fluoride limits in drinking water based on estimated daily fluoride intake in the Upper East Region, Ghana. Sci. Total Environ. 2015, 532, 127–137. [Google Scholar] [CrossRef] [PubMed]
- Radzki, D.; Wilhelm-Waglarz, M.; Pruska, K.; Kusiak, A.; Ordyniec-Kwa?nica, I. A Fresh Look at Mouthwashes—What Is Inside and What Is It For? Int. J. Environ. Res. Public Health 2022, 19, 3926. [Google Scholar] [CrossRef] [PubMed]
- Viragh, E.; Viragh, H.; Laczka, J.; Coldea, V. Health Effects of Occupational Exposure to Fluorine and Its Compounds in a Small-Scale Enterprise. Ind. Health 2006, 44, 64–68. [Google Scholar] [CrossRef] [PubMed]
- Whitford, G.M. Fluoride in Dental Products: Safety Considerations. J. Dent. Res. 1987, 66, 1056–1060. [Google Scholar] [CrossRef] [PubMed]
- NIOSH; Centers for Disease Control and Prevention (CDC). NIOSH Pocket Guide to Chemical Hazards: Sodium Fluoride (as F). 2019. Available online: https://www.cdc.gov/niosh/npg/npgd0563.html (accessed on 30 July 2026).
- OSHA; U.S. Department of Labor. Permissible Exposure Limits—Annotated Tables: Fluorides (as F). 2025. Available online: https://www.osha.gov/annotated-pels/table-z-1 (accessed on 30 July 2026).
- ATSDR; U.S. Department of Health and Human Services. Toxicological Profile for Fluorides, Hydrogen Fluoride, and Fluorine; Public Health Service: Atlanta, GA, USA, 2003. Available online: https://www.atsdr.cdc.gov/toxprofiles/tp11.pdf (accessed on 30 July 2026).
- Muneeswaran, T.; Bhatt, T.; Park, S.H.; Maruthupandy, M.; Kim, M.; Mathur, V.; Lee, J.-H.; Kim, M.-S.; Cho, W.-S. Polyethylene glycol used as a dispersant potentiates the toxicity of insecticides in mammalian cells rather than insects. Environ. Int. 2025, 196, 109307. [Google Scholar] [CrossRef] [PubMed]
- Jeon, K.; Yu, I.J.; Ahn, K.-H. Evaluation of newly developed nose-only inhalation exposure chamber for nanoparticles. Inhal. Toxicol. 2012, 24, 550–556. [Google Scholar] [CrossRef] [PubMed]
- Lee, D.-K.; Kim, G.; Maruthupandy, M.; Lee, K.; Cho, W.-S. Multimodal pulmonary clearance kinetics of carbon black nanoparticles deposited in the lungs of rats: The role of alveolar macrophages. Part. Fibre Toxicol. 2024, 21, 32. [Google Scholar] [CrossRef] [PubMed]
- Gillis, E.P.; Eastman, K.J.; Hill, M.D.; Donnelly, D.J.; Meanwell, N.A. Applications of Fluorine in Medicinal Chemistry. J. Med. Chem. 2015, 58, 8315–8359. [Google Scholar] [CrossRef] [PubMed]
- Lee, S.; Hwang, S.-H.; Jeong, J.; Han, Y.; Kim, S.-H.; Lee, D.-K.; Lee, H.-S.; Chung, S.-T.; Jeong, J.; Roh, C.; et al. Nickel oxide nanoparticles can recruit eosinophils in the lungs of rats by the direct release of intracellular eotaxin. Part. Fibre Toxicol. 2016, 13, 30. [Google Scholar] [CrossRef] [PubMed]
- Cho, W.S.; Duffin, R.; Howie, S.E.; Scotton, C.J.; Wallace, W.A.; Macnee, W.; Bradley, M.; Megson, I.L.; Donaldson, K. Progressive severe lung injury by zinc oxide nanoparticles; the role of Zn2+ dissolution inside lysosomes. Part. Fibre Toxicol. 2011, 8, 27. [Google Scholar] [CrossRef] [PubMed]
- OECD. Test No. 413: Subchronic Inhalation Toxicity: 90-Day Study; OECD: Paris, France, 2018. [Google Scholar]
- OECD. Test No. 412: Subacute Inhalation Toxicity: 28-Day Study; OECD: Paris, France, 2018. [Google Scholar]
- Cho, W.S.; Duffin, R.; Poland, C.A.; Howie, S.E.; MacNee, W.; Bradley, M.; Megson, I.L.; Donaldson, K. Metal oxide nanoparticles induce unique inflammatory footprints in the lung: Important implications for nanoparticle testing. Environ. Health Perspect. 2010, 118, 1699–1706. [Google Scholar] [CrossRef] [PubMed]
- Fujisawa, T.; Kato, Y.; Atsuta, J.; Terada, A.; Iguchi, K.; Kamiya, H.; Yamada, H.; Nakajima, T.; Miyamasu, M.; Hirai, K. Chemokine production by the BEAS-2B human bronchial epithelial cells: Differential regulation of eotaxin, IL-8, and RANTES by TH2- and TH1-derived cytokines. J. Allergy Clin. Immunol. 2000, 105, 126–133. [Google Scholar] [CrossRef] [PubMed]
- Hirano, S.; Ando, M.; Kanno, S. Inflammatory responses of rat alveolar macrophages following exposure to fluoride. Arch. Toxicol. 1999, 73, 310–315. [Google Scholar] [CrossRef] [PubMed]
- Song, C.; Shi, D.; Chang, K.; Li, X.; Dong, Q.; Ma, X.; Wang, X.; Guo, Z.; Liu, Y.; Wang, J. Sodium fluoride activates the extrinsic apoptosis via regulating NOX4/ROS-mediated p53/DR5 signaling pathway in lung cells both in vitro and in vivo. Free Radic. Biol. Med. 2021, 169, 137–148. [Google Scholar] [CrossRef] [PubMed]
- Wei, M.; Ye, Y.; Ali, M.M.; Chamba, Y.; Tang, J.; Shang, P. Effect of Fluoride on Cytotoxicity Involved in Mitochondrial Dysfunction: A Review of Mechanism. Front. Vet. Sci. 2022, 9, 850771. [Google Scholar] [CrossRef] [PubMed]
- Lemiere, C.; Lavoie, G.; Doyen, V.; Vandenplas, O. Irritant-Induced Asthma. J. Allergy Clin. Immunol. Pract. 2022, 10, 2799–2806. [Google Scholar] [CrossRef] [PubMed]
- Abdel-Gawad, F.A.-R.; Ashmawy, M.H.; Zaki, S.M.; Abdel-Fatah, G.H. Experimental research Lung damage after long-term exposure of adult rats to sodium fluoride. Arch. Med. Sci. 2014, 10, 1035–1040. [Google Scholar] [CrossRef] [PubMed]
- Ameeramja, J.; Perumal, E. Possible Modulatory Effect of Tamarind Seed Coat Extract on Fluoride-Induced Pulmonary Inflammation and Fibrosis in Rats. Inflammation 2018, 41, 886–895. [Google Scholar] [CrossRef] [PubMed]
- Johnston, N.R.; Strobel, S.A. Principles of fluoride toxicity and the cellular response: A review. Arch. Toxicol. 2020, 94, 1051–1069. [Google Scholar] [CrossRef] [PubMed]
- Qu, H.; Wei, M. The effect of fluoride contents in fluoridated hydroxyapatite on osteoblast behavior. Acta Biomater. 2006, 2, 113–119. [Google Scholar] [CrossRef] [PubMed]
- Ahuja, K.; Sotoudeh, H.; Galgano, S.J.; Singh, R.; Gupta, N.; Gaddamanugu, S.; Choudhary, G. 18F-Sodium Fluoride PET: History, Technical Feasibility, Mechanism of Action, Normal Biodistribution, and Diagnostic Performance in Bone Metastasis Detection Compared with Other Imaging Modalities. J. Nucl. Med. Technol. 2020, 48, 9–16. [Google Scholar] [CrossRef] [PubMed]
- Smiley, R.M.; Ornstein, E.; Pantuck, E.J.; Pantuck, C.B.; Matteo, R.S. Metabolism of desflurane and isoflurane to fluoride ion in surgical patients. Can. J. Anaesth. 1991, 38, 965–968. [Google Scholar] [CrossRef] [PubMed]
- Choi, Y.; Kim, H.R.; Kwon, J.-H. Concentration-dependent aerosol size alters regional deposition and inhalation dose translation. Sci. Rep. 2026, 16, 5183. [Google Scholar] [CrossRef] [PubMed]
- Varghese, S.K.; Gangamma, S. Particle Deposition in Human Respiratory Tract: Effect of Water-Soluble Fraction. Aerosol Air Qual. Res. 2006, 6, 360–379. [Google Scholar] [CrossRef]
- Lippmann, M.; Yeates, D.B.; Albert, R.E. Deposition, retention, and clearance of inhaled particles. Br. J. Ind. Med. 1980, 37, 337–362. [Google Scholar] [CrossRef] [PubMed]
- Fuentes, N.; Silveyra, P. Endocrine regulation of lung disease and inflammation. Exp. Biol. Med. 2018, 243, 1313–1322. [Google Scholar] [CrossRef] [PubMed]
- Han, J.; Kiss, L.; Mei, H.; Remete, A.M.; Ponikvar-Svet, M.; Sedgwick, D.M.; Roman, R.; Fustero, S.; Moriwaki, H.; Soloshonok, V.A. Chemical Aspects of Human and Environmental Overload with Fluorine. Chem. Rev. 2021, 121, 4678–4742. [Google Scholar] [CrossRef] [PubMed]
- Rigler, M.W.; Longo, W.E.; Sauerhoff, M.W. Exposure to fluoropolymers and VOCs during spray sealant product use. Inhal. Toxicol. 2011, 23, 641–657. [Google Scholar] [CrossRef] [PubMed]
- Prado, E.; Wurtz, T.; Ferbus, D.; Shabana, E.-H.; Forest, N.; Berdal, A. Sodium fluoride influences the expression of keratins in cultured keratinocytes. Cell Biol. Toxicol. 2011, 27, 69–81. [Google Scholar] [CrossRef] [PubMed]
- Karaoz, E.; Oncu, M.; Gulle, K.; Kanter, M.; Gultekin, F.; Karaoz, S.; Mumcu, E. Effect of chronic fluorosis on lipid peroxidation and histology of kidney tissues in first- and second-generation rats. Biol. Trace Elem. Res. 2004, 102, 199–208. [Google Scholar] [CrossRef] [PubMed]
- Hodge, H.C.; Smith, F.A. Occupational Fluoride Exposure. J. Occup. Environ. Med. 1977, 19, 12–39. [Google Scholar] [CrossRef] [PubMed]
- EPA. National Primary Drinking Water Regulations: Fluoride. 2023. Available online: https://www.epa.gov/ground-water-and-drinking-water/national-primary-drinking-water-regulations#Inorganic (accessed on 30 July 2026).